Medical dosimetry is the calculation of absorbed dose and optimization of dose delivery in medical examinations and treatments. Medical Dosimetry
Ionizing radiation – hazard symbol
Radiation dosimetry is the measurement, calculation and assessment of the absorbed doses and assigning those doses to individuals. It is the science and practice that attempts to quantitatively relate specific measures made in a radiation field to chemical and/or biological changes that the radiation would produce in a target.
Medical Dosimetry
Medical dosimetry is the calculation of absorbed dose and optimization of dose delivery in medical examinations and treatments. In general, radiation exposures from medical diagnostic examinations are low (especially in diagnostic uses). Doses may be also high (only for therapeutic uses), but in each case, they must be always justified by the benefits of accurate diagnosis of possible disease conditions or by benefits of accurate treatment. These doses include contributions from medical and dental diagnostic radiology (diagnostic X-rays), clinical nuclear medicine and radiation therapy. Medical dosimetry is often performed by a professional health physicist with specialized training in that field. In order to plan the delivery of radiation therapy, the radiation produced by the sources is usually characterized with percentage depth dose curves and dose profiles measured by a medical physicist.
The medical use of ionizing radiation remains a rapidly changing field. In any case, usefulness of ionizing radiation must be balanced with its hazards. Nowadays a compromise was found and most of uses of radiation are optimized. Today it is almost unbelievable that x-rays was, at one time, used to find the right pair of shoes (i.e. shoe-fitting fluoroscopy). Measurements made in recent years indicate that the doses to the feet were in the range 0.07 – 0.14 Gy for a 20 second exposure. This practice was halted when the risks of ionizing radiation were better understood.
In the following points we try to express enormous ranges of radiation exposure as well as a few doses from medical sources.
1 µSv – Eating one banana
1 µSv – Extremity (hand, foot, etc.) X-ray
5 µSv – Dental X-ray
10 µSv – Average daily dose received from natural background
40 µSv – A 5-hour airplane flight
100 µSv – Chest X-ray
600 µSv – mammogram
1 000 µSv – Dose limit for individual members of the public, total effective dose per annum
3 650 µSv – Average yearly dose received from natural background
5 800 µSv – Chest CT scan
10 000 µSv – Average yearly dose received from natural background in Ramsar, Iran
20 000 µSv – single full-body CT scan
80 000 µSv – The annual local dose to localized spots at the bifurcations of segmental bronchi in the lungs caused by smoking cigarettes (1.5 packs/day).
175 000 µSv – Annual dose from natural radiation on a monazite beach near Guarapari, Brazil.
5 000 000 µSv – Dose that kills a human with a 50% risk within 30 days (LD50/30), if the dose is received over a very short duration.
As can be seen, low-level doses are common for everyday life.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Dosimetry
We hope, this article, Medical Dosimetry, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Personal dosimetry is a key part of radiation dosimetry. Personal dosimetry is used primarily (but not exclusively) to determine doses to individuals who are exposed to radiation related to their work activities. Radiation Dosimetry
Radiation dosimetry is the measurement, calculation and assessment of the absorbed doses and assigning those doses to individuals. It is the science and practice that attempts to quantitatively relate specific measures made in a radiation field to chemical and/or biological changes that the radiation would produce in a target.
Personal Dosimetry
EPD – Electronic Personal Dosimeter
Personal dosimetry is a key part of radiation dosimetry. Personal dosimetry is used primarily (but not exclusively) to determine doses to individuals who are exposed to radiation related to their work activities. These doses are usually measured by devices known as dosimeters. Dosimeters usually record a dose, which is the absorbed radiation energy measured in grays (Gy) or the equivalent dose measured in sieverts (Sv). A personal dosimeter is dosimeter, that is worn at the surface of the body by the person being monitored, and it records of the radiation dose received. Personal dosimetry techniques vary and depend partly on whether the source of radiation is outside the body (external) or taken into the body (internal). Personal dosimeters are used to measure external radiation exposures. Internal exposures are typically monitored by measuring the presence of nuclear substances in the body, or by measuring nuclear substances excreted by the body.
Commercially available dosimeters range from low-cost, passive devices that store personnel dose information for later readout, to more expensive, battery operated devices that display immediate dose and dose rate information (typically an electronic personal dosimeter). Readout method, dose measurement range, size, weight, and price are important selection factors.
There are two kinds of dosimeters:
Passive Dosimeters. Commonly used passive dosimeters are the Thermo Luminescent Dosimeter (TLD) and the film badge. A passive dosimeter produces a radiation-induced signal, which is stored in the device. The dosimeter is then processed and the output is analyzed.
Active Dosimeters. To get a real time value of your exposure you can instead use an active dosimeter, typically an electronic personal dosimeter (EPD). An active dosimeter produces a radiation-induced signal and displays a direct reading of the detected dose or dose rate in real time.
The passive and the active dosimeters are often used together to complement each other. To estimate effective doses, dosimeters must be worn on a position of the body representative of its exposure, typically between the waist and the neck, on the front of the torso, facing the radioactive source. Dosimeters are usually worn on the outside of clothing, around the chest or torso to represent dose to the “whole body”. Dosimeters may also be worn on the extremities or near the eye to measure equivalent dose to these tissues.
The personal dosimeters in use today are not absolute instruments, but reference instruments. That means , they must be periodically calibrated. When a reference dosimeter is calibrated, a calibration factor can be determined. This calibration factor relates the exposure quantity to the reported dose. Validity of the calibration is demonstrated by maintaining traceability of the source used to calibrate the dosimeter. The traceability is achieved by comparison of the source with a “primary standard” at a reference calibration centre. In monitoring of individuals, the values of these operational quantities are taken as a sufficiently precise assessment of effective dose and skin dose, respectively, in particular, if their values are below the protection limits.
Example – Electronic Personal Dosimeter
An electronic personal dosimeter is modern dosimeter, which can give a continuous readout of cumulative dose and current dose rate, and can warn the person wearing it when a specified dose rate or a cumulative dose is exceeded. EPDs are especially useful in high dose areas where residence time of the wearer is limited due to dose constraints.
Types of EPDs
EPDs are battery powered and most use either a small Geiger-Mueller (GM) tube or a semiconductor in which ionizing radiation releases charges resulting in measurable electric current.
G-M counter. A Geiger counter consists of a Geiger-Müller tube (the sensing element which detects the radiation) and the processing electronics, which displays the result. G-M counters are mainly used for portable instrumentation due to its sensitivity, simple counting circuit, and ability to detect low-level radiation. Because of the large avalanche induced by any ionization, a Geiger counter takes a long time (about 1 ms) to recover between successive pulses. Therefore, Geiger counters are not able to measure high radiation rates due to the “dead time” of the tube.
Semiconductor Detector. Semiconductor detectors are based on ionization in a solid (e.g. silicon) and include different types of solid-state devices with two terminals called diodes. For example a silicon diode, which has a p-i-n structure in which the intrinsic (i) region is sensitive to ionizing radiation, particularly X rays and gamma rays. Under reverse bias, an electric field extends across the intrinsic or depleted region. In this case, negative voltage is applied to the p-side and positive to the second one. Holes in the p-region are attracted from the junction towards the p contact and similarly for electrons and the n contact.
Scintillation Detector. Some EPDs use a scintillating crystal such as sodium iodide (NaI) or cesium iodide (CsI) with a photodiode or photomultiplier tube to measure photons released by radiation.
Characteristics of EPDs
The electronic personal dosimeter, EPD, is able to display a direct reading of the detected dose or dose rate in real time. Electronic dosimeters may be used as a supplemental dosimeter as well a primary dosimeter. The passive dosimeters and the electronic personal dosimeters are often used together to complement each other. To estimate effective doses, dosimeters must be worn on a position of the body representative of its exposure, typically between the waist and the neck, on the front of the torso, facing the radioactive source. Dosimeters are usually worn on the outside of clothing, around the chest or torso to represent dose to the “whole body”. Dosimeters may also be worn on the extremities or near the eye to measure equivalent dose to these tissues.
The dosimeter can be reset, usually after taking a reading for record purposes, and thereby re-used multiple times. The EPDs have a top mounted display to make them easy to read when they are clipped to your breast pocket. The digital display gives both dose and dose rate information usually in mSv and mSv/h. The EPD has a dose rate alarm, and a dose alarm. These alarms are programmable. Different alarms can be set for different activities.
For example:
dose rate alarm at 100 μSv/h,
dose alarm: 100 μSv.
If an alarm set point is reached, the relevant display flashes along with a red light, and quite a piercing noise is generated. You can clear the dose rate alarm by retreating to a lower radiation field, but you cannot clear the dose alarm until you get to a EPD reader. EPDs can also give a bleep for every 1 or 10 μSv they register. This gives you an audible indication of the radiation fields. Some EPDs have wireless communication capabilities. EPDs are capable of measuring a wide radiation dose range from routine (μSv) levels to emergency levels (hundreds mSv or units of Sieverts) with high precision, and may display the exposure rate as well as accumulated exposure values. Of the dosimeter technologies, electronic personal dosimeters are generally the most expensive, largest in size, and the most versatile.
DMC 3000 – Mirion Technologies Inc.
The DMC 3000 is an electronic radiation dosimeter, EPD, that provides dose and ambient dose rate readings for deep dose equivalent Hp(10). It is one of the most used EPDs on the market. It uses a Si chipdetector with gamma sensitivity of 180 cps/R/h. This electronic personal dosimeter has the following characteristics:
Energy response (X-ray and gamma) from 15 keV to 7 Mev.
Dose measurement display range: between 1 μSv and 10 Sv.
Rate measurement display range: between 10 μSv/hr and 10 Sv/h.
The device measures 3.3 x 1.9 x 0.7 inches and has options for being clipped to a pocket, belt, or lanyard. It is powered with rechargeable or AAA batteries with a battery life of up to 2,500 hours of continuous use. Audible and visual indicators signal a low battery condition. The device has a backlit, eight-digit LCD display; two-button navigation; and visual LED, audible, and vibrating alarm indicators. Calibration is expected to last 9 months under routine use and 2 years in storage. Data is stored in nonvolatile memory. The operating range for the dosimeter is from 14°F to 122°F and up to 90 percent relative humidity. It is drop tested to 1.5 meters. The DMC 3000 has optional external modules that expand the device’s detection and communication capabilities. These include a beta module that provides Hp(0,07) for beta radiation measurement; a neutron module that provides Hp(10) neutron radiation measurement; and a telemetry module that allows transmission of data to an external station.
See also: The Radiation Dosimeters for Response and Recovery Market Survey Report. National Urban Security Technology Laboratory. SAVER-T-MSR-4. <available from: https://www.dhs.gov/sites/default/files/publications/Radiation-Dosimeters-Response-Recovery-MSR_0616-508_0.pdf>.
Radiation Dose Measuring and Monitoring
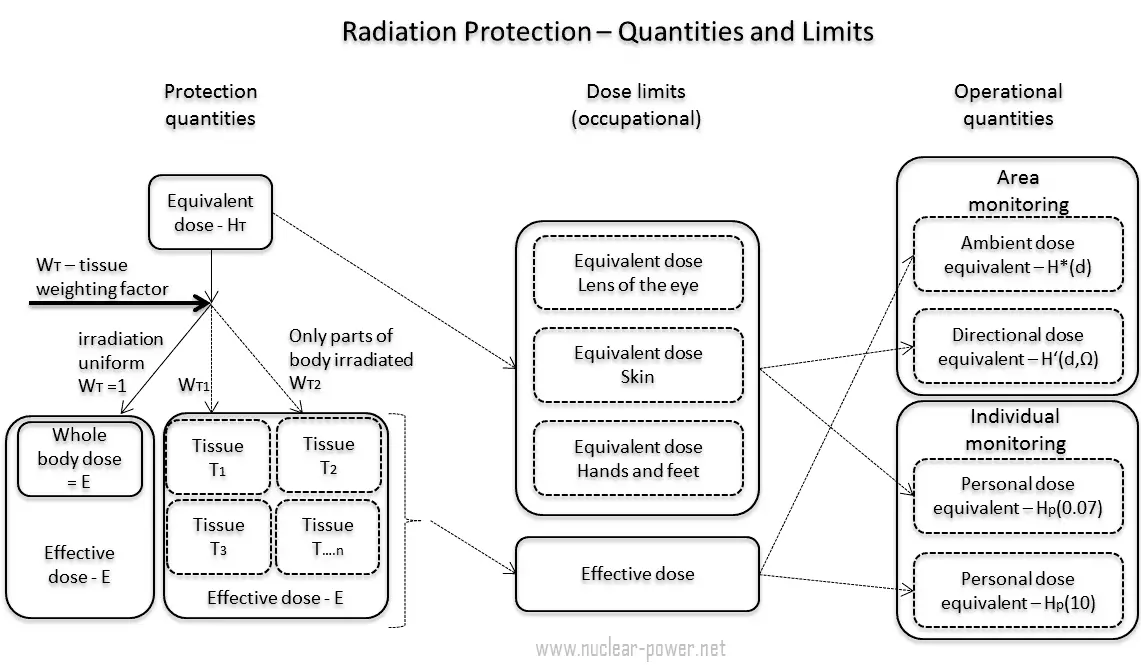
In previous chapters, we described the equivalent dose and the effective dose. But these doses are not directly measurable. For this purpose, the ICRP has introduced and defined a set of operational quantities, which can be measured and which are intended to provide a reasonable estimate for the protection quantities. These quantities aim to provide a conservative estimate for the value of the protection quantities related to an exposure avoiding both underestimation and too much overestimation.
Numerical links between these quantities is represented by conversion coefficients, which are defined for a reference person. It is very important that an internationally agreed set of conversion coefficients is available for general use in radiological protection practice for occupational exposures and exposures of the public. For the calculation of conversion coefficients for external exposure, computational phantoms are used for dose assessment in various radiation fields. For the calculation of dose coefficients from intakes of radionuclides, biokinetic models for radionuclides, reference physiological data, and computational phantoms are used.
A set of evaluated data of conversion coefficients for protection, and operational quantities for external exposure to mono-energetic photon, neutron, and electron radiation under specific irradiation conditions is published in reports (ICRP, 1996b, ICRU, 1997).
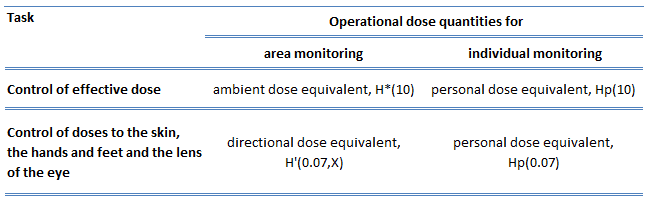
In general, the ICRP defines operational quantities for area and individual monitoring of external exposures. The operational quantities for area monitoring are:
Ambient dose equivalent, H*(10). The ambient dose equivalent is an operational quantity for area monitoring of strongly penetrating radiation.
Directional dose equivalent, H’ (d,Ω). The directional dose equivalent is an operational quantity for area monitoring of weakly penetrating radiation.
Personal dose equivalent, Hp(0.07). The Hp(0.07) dose equivalent is an operational quantity for individual monitoring for the assessment of the dose to the skin and to the hands and feet.
Personal dose equivalent, Hp(10). The Hp(10) dose equivalent is an operational quantity for individual monitoring for the assessment of effective dose.
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Dose limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
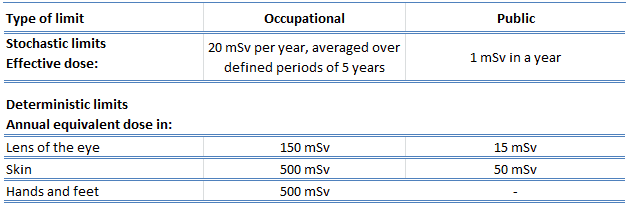
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Dosimetry
We hope, this article, Personal Dosimetry, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Internal dosimetry assessment relies on a variety of monitoring, bio-assay or radiation imaging techniques. Internal Dosimetry – Internal Exposure
Ionizing radiation – hazard symbol
Radiation dosimetry is the measurement, calculation and assessment of the absorbed doses and assigning those doses to individuals. It is the science and practice that attempts to quantitatively relate specific measures made in a radiation field to chemical and/or biological changes that the radiation would produce in a target.
Internal Dosimetry
If the source of radiation is inside our body, we say, it is internal exposure. The intake of radioactive material can occur through various pathways such as ingestion of radioactive contamination in food or liquids. Protection from internal exposure is more complicated. Most radionuclides will give you much more radiation dose if they can somehow enter your body, than they would if they remained outside. Internal dosimetry assessment relies on a variety of monitoring, bio-assay or radiation imaging techniques.
Medical dosimetry is the calculation of absorbed dose and optimization of dose delivery in medical examinations and treatments. In general, radiation exposures from medical diagnostic examinations are low (especially in diagnostic uses). Doses may be also high (only for therapeutic uses), but in each case, they must be always justified by the benefits of accurate diagnosis of possible disease conditions or by benefits of accurate treatment. These doses include contributions from medical and dental diagnostic radiology (diagnostic X-rays), clinical nuclear medicine and radiation therapy. Medical dosimetry is often performed by a professional health physicist with specialized training in that field. In order to plan the delivery of radiation therapy, the radiation produced by the sources is usually characterized with percentage depth dose curves and dose profiles measured by a medical physicist.
The medical use of ionizing radiation remains a rapidly changing field. In any case, usefulness of ionizing radiation must be balanced with its hazards. Nowadays a compromise was found and most of uses of radiation are optimized. Today it is almost unbelievable that x-rays was, at one time, used to find the right pair of shoes (i.e. shoe-fitting fluoroscopy). Measurements made in recent years indicate that the doses to the feet were in the range 0.07 – 0.14 Gy for a 20 second exposure. This practice was halted when the risks of ionizing radiation were better understood.
A whole-body counter is an instrument that measures the amounts of gamma-emitting radionuclides in the body (i.e. it is a gamma spectrometer). In nuclear facilities, these counters are used for measurement of radioactivity within the human body, that means, for internal contamination measurements. This must not be confused with a “whole body monitor” which used for personnel exit monitoring, which is the term used in radiation protection for checking for external contamination of a whole body of a person leaving a radioactive contamination controlled area. Whole-body counters are very sensitive devices and therefore they are often surrounded by large quantities of lead shielding to reduce the background radiation. A whole-body counter consists, for example, of a stand-up booth with two large-area NaI scintillation detectors. The upper detector monitors lungs, the lower detector monitors the gastrointestinal tract.
It must be noted, all people also have some radioactive isotopes inside their bodies from birth. These isotopes are especially potassium-40, carbon-14 and also the isotopes of uranium and thorium. The average annual radiation dose to a person from internal radioactive materials other than radon is about 0.3 mSv/year of which:
2 mSv/year comes from potassium-40,
12 mSv/year comes from the uranium and thorium series,
12 μSv/year comes from carbon-40.
The variation in radiation dose from one person to another is not as great, but it is detected also by a whole-body counter.
Gamma Spectroscopy
As was written, the study and analysis of gamma ray spectra for scientific and technical use is called gamma spectroscopy, and gamma ray spectrometers are the instruments which observe and collect such data. A gamma ray spectrometer (GRS) is a sophisticated device for measuring the energy distribution of gamma radiation. For the measurement of gamma rays above several hundred keV, there are two detector categories of major importance, inorganic scintillators as NaI(Tl) and semiconductor detectors. In the previous articles, we described the gamma spectroscopy using scintillation detector, which consists of a suitable scintillator crystal, a photomultiplier tube, and a circuit for measuring the height of the pulses produced by the photomultiplier. The advantages of a scintillation counter are its efficiency (large size and high density) and the high precision and counting rates that are possible. Due to the high atomic number of iodine, a large number of all interactions will result in complete absorption of gamma-ray energy, so the photo fraction will be high.
HPGe detector with LN2 cryostat Source: canberra.com
But if a perfect energy resolution is required, we have to use germanium-based detector, such as the HPGe detector. Germanium-based semiconductor detectors are most commonly used where a very good energy resolution is required, especially for gamma spectroscopy, as well as x-ray spectroscopy. In gamma spectroscopy, germanium is preferred due to its atomic number being much higher than silicon and which increases the probability of gamma ray interaction. Moreover, germanium has lower average energy necessary to create an electron-hole pair, which is 3.6 eV for silicon and 2.9 eV for germanium. This also provides the latter a better resolution in energy. The FWHM (full width at half maximum) for germanium detectors is a function of energy. For a 1.3 MeV photon, the FWHM is 2.1 keV, which is very low.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Dosimetry
We hope, this article, Internal Dosimetry, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
External dosimetry is based on measurements with a dosimeter, or inferred from measurements made by other radiological protection instruments. Radiation Dosimetry
Ionizing radiation – hazard symbol
Radiation dosimetry is the measurement, calculation and assessment of the absorbed doses and assigning those doses to individuals. It is the science and practice that attempts to quantitatively relate specific measures made in a radiation field to chemical and/or biological changes that the radiation would produce in a target.
External Dosimetry
External exposure is radiation that comes from outside our body and interacts with us. In this case, we analyze predominantly exposure from gamma rays and beta particles, since alpha particles, in general, constitute no external exposure hazard because the particles generally do not pass through skin. Since photons and beta interact through electromagnetic forces and neutrons interact through nuclear forces, their detection methods and dosimetry are substantially different. The source of radiation can be, for example, a piece of equipment that produces the radiation like a container with a radioactive materials, or like an x-ray machine. External dosimetry is based on measurements with a dosimeter, or inferred from measurements made by other radiological protection instruments.
Personal Dosimetry
EPD – Electronic Personal Dosimeter
Personal dosimetry is a key part of external radiation dosimetry. Personal dosimetry is used primarily (but not exclusively) to determine doses to individuals who are exposed to radiation related to their work activities. These doses are usually measured by devices known as dosimeters. Dosimeters usually record a dose, which is the absorbed radiation energy measured in grays (Gy) or the equivalent dose measured in sieverts (Sv). A personal dosimeter is dosimeter, that is worn at the surface of the body by the person being monitored, and it records of the radiation dose received. Personal dosimetry techniques vary and depend partly on whether the source of radiation is outside the body (external) or taken into the body (internal). Personal dosimeters are used to measure external radiation exposures. Internal exposures are typically monitored by measuring the presence of nuclear substances in the body, or by measuring nuclear substances excreted by the body.
Commercially available dosimeters range from low-cost, passive devices that store personnel dose information for later readout, to more expensive, battery operated devices that display immediate dose and dose rate information (typically an electronic personal dosimeter). Readout method, dose measurement range, size, weight, and price are important selection factors.
Protection against External Exposure
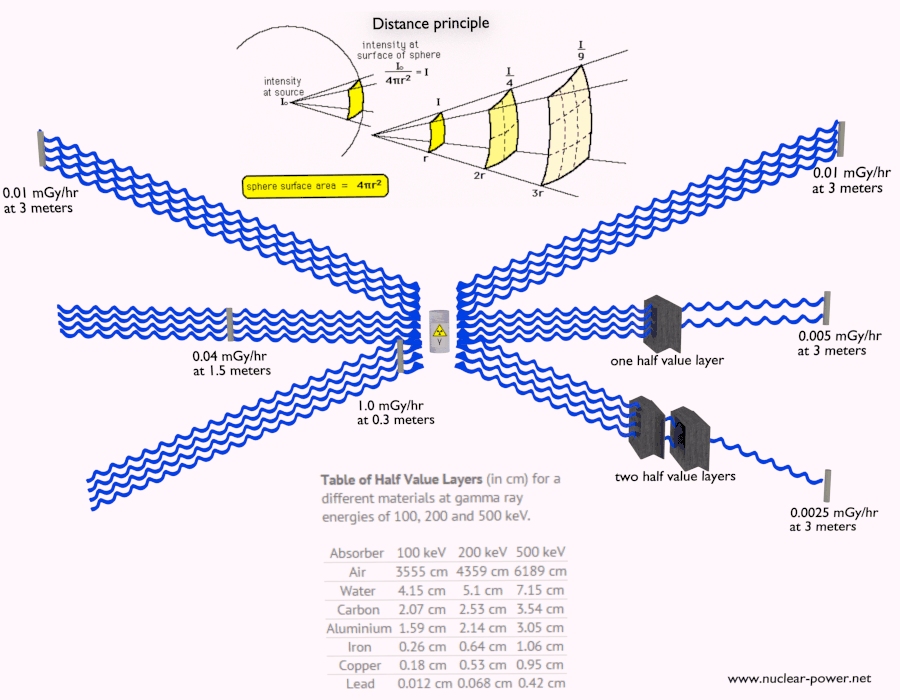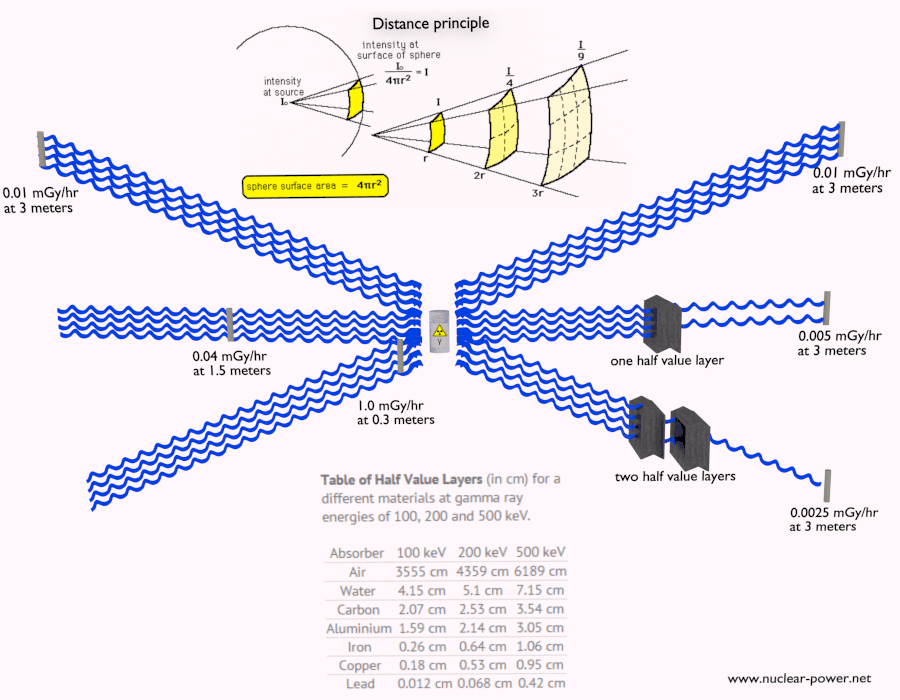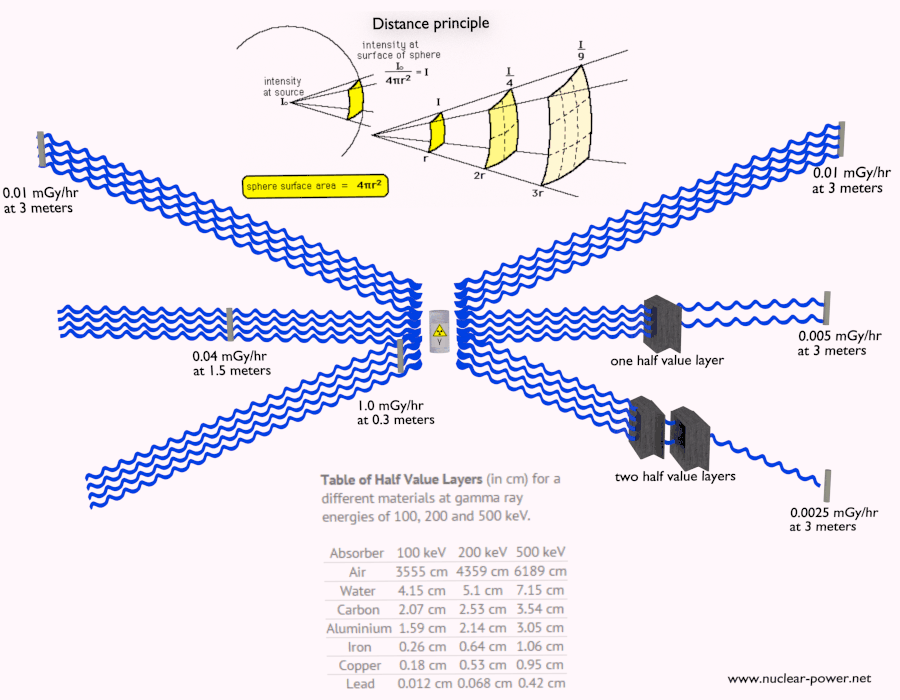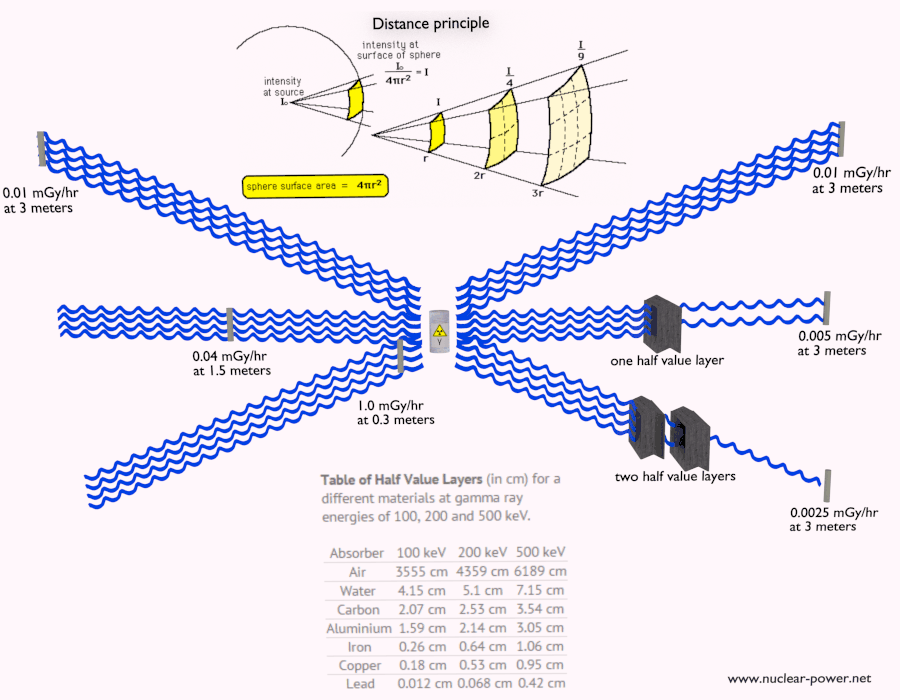
In radiation protection there are three ways how to protect people from identified external radiation sources:
Principles of Radiation Protection – Time, Distance, Shielding
Limiting Time. The amount of radiation exposure depends directly (linearly) on the time people spend near the source of radiation. The dose can be reduced by limiting exposure time.
Distance. The amount of radiation exposure depends on the distance from the source of radiation. Similarly to a heat from a fire, if you are too close, the intensity of heat radiation is high and you can get burned. If you are at the right distance, you can withstand there without any problems and moreover it is comfortable. If you are too far from heat source, the insufficiency of heat can also hurt you. This analogy, in a certain sense, can be applied to radiation also from radiation sources.
Shielding. Finally, if the source is too intensive and time or distance do not provide sufficient radiation protection, the shielding must be used. Radiation shielding usually consist of barriers of lead, concrete or water. There are many many materials, which can be used for radiation shielding, but there are many many situations in radiation protection. It highly depends on the type of radiation to be shielded, its energy and many other parametres. For example, even depleted uranium can be used as a good protection from gamma radiation, but on the other hand uranium is absolutely inappropriate shielding of neutron radiation.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Dosimetry
We hope, this article, External Dosimetry, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Radiation dosimetry is the measurement, calculation and assessment of the absorbed doses and assigning those doses to individuals. Radiation Dosimetry
Ionizing radiation – hazard symbol
Radiation dosimetry is the measurement, calculation and assessment of the absorbed doses and assigning those doses to individuals. It is the science and practice that attempts to quantitatively relate specific measures made in a radiation field to chemical and/or biological changes that the radiation would produce in a target.
Since there are two types of radiation exposure, external and internal exposure, dosimetry may be also categorized as:
External Dosimetry. External exposure is radiation that comes from outside our body and interacts with us. In this case, we analyze predominantly exposure from gamma rays and beta particles, since alpha particles, in general, constitute no external exposure hazard because the particles generally do not pass through skin. Since photons and beta interact through electromagnetic forces and neutrons interact through nuclear forces, their detection methods and dosimetry are substantially different. The source of radiation can be, for example, a piece of equipment that produces the radiation like a container with a radioactive materials, or like an x-ray machine. External dosimetry is based on measurements with a dosimeter, or inferred from measurements made by other radiological protection instruments.
HPGe detector with LN2 cryostat, which can be used in whole-body counters. Source: canberra.com
Internal Dosimetry. If the source of radiation is inside our body, we say, it is internal exposure. The intake of radioactive material can occur through various pathways such as ingestion of radioactive contamination in food or liquids. Protection from internal exposure is more complicated. Most radionuclides will give you much more radiation dose if they can somehow enter your body, than they would if they remained outside. Internal dosimetry assessment relies on a variety of monitoring, bio-assay or radiation imaging techniques.
Personal Dosimetry
EPD – Electronic Personal Dosimeter
Personal dosimetry is a key part of radiation dosimetry. Personal dosimetry is used primarily (but not exclusively) to determine doses to individuals who are exposed to radiation related to their work activities. These doses are usually measured by devices known as dosimeters. Dosimeters usually record a dose, which is the absorbed radiation energy measured in grays (Gy) or the equivalent dose measured in sieverts (Sv). A personal dosimeter is dosimeter, that is worn at the surface of the body by the person being monitored, and it records of the radiation dose received. Personal dosimetry techniques vary and depend partly on whether the source of radiation is outside the body (external) or taken into the body (internal). Personal dosimeters are used to measure external radiation exposures. Internal exposures are typically monitored by measuring the presence of nuclear substances in the body, or by measuring nuclear substances excreted by the body.
Commercially available dosimeters range from low-cost, passive devices that store personnel dose information for later readout, to more expensive, battery operated devices that display immediate dose and dose rate information (typically an electronic personal dosimeter). Readout method, dose measurement range, size, weight, and price are important selection factors.
There are two kinds of dosimeters:
Passive Dosimeters. Commonly used passive dosimeters are the Thermo Luminescent Dosimeter (TLD) and the film badge. A passive dosimeter produces a radiation-induced signal, which is stored in the device. The dosimeter is then processed and the output is analyzed.
Active Dosimeters. To get a real time value of your exposure you can instead use an active dosimeter, typically an electronic personal dosimeter (EPD). An active dosimeter produces a radiation-induced signal and displays a direct reading of the detected dose or dose rate in real time.
The passive and the active dosimeters are often used together to complement each other. To estimate effective doses, dosimeters must be worn on a position of the body representative of its exposure, typically between the waist and the neck, on the front of the torso, facing the radioactive source. Dosimeters are usually worn on the outside of clothing, around the chest or torso to represent dose to the “whole body”. Dosimeters may also be worn on the extremities or near the eye to measure equivalent dose to these tissues.
The personal dosimeters in use today are not absolute instruments, but reference instruments. That means , they must be periodically calibrated. When a reference dosimeter is calibrated, a calibration factor can be determined. This calibration factor relates the exposure quantity to the reported dose. Validity of the calibration is demonstrated by maintaining traceability of the source used to calibrate the dosimeter. The traceability is achieved by comparison of the source with a “primary standard” at a reference calibration centre. In monitoring of individuals, the values of these operational quantities are taken as a sufficiently precise assessment of effective dose and skin dose, respectively, in particular, if their values are below the protection limits.
Example - Electronic Personal Dosimeter
EPD – Electronic Personal Dosimeter
An electronic personal dosimeter is modern dosimeter, which can give a continuous readout of cumulative dose and current dose rate, and can warn the person wearing it when a specified dose rate or a cumulative dose is exceeded. EPDs are especially useful in high dose areas where residence time of the wearer is limited due to dose constraints.
Types of EPDs
EPDs are battery powered and most use either a small Geiger-Mueller (GM) tube or a semiconductor in which ionizing radiation releases charges resulting in measurable electric current.
G-M counter. A Geiger counter consists of a Geiger-Müller tube (the sensing element which detects the radiation) and the processing electronics, which displays the result. G-M counters are mainly used for portable instrumentation due to its sensitivity, simple counting circuit, and ability to detect low-level radiation. Because of the large avalanche induced by any ionization, a Geiger counter takes a long time (about 1 ms) to recover between successive pulses. Therefore, Geiger counters are not able to measure high radiation rates due to the “dead time” of the tube.
Semiconductor Detector. Semiconductor detectors are based on ionization in a solid (e.g. silicon) and include different types of solid-state devices with two terminals called diodes. For example a silicon diode, which has a p-i-n structure in which the intrinsic (i) region is sensitive to ionizing radiation, particularly X rays and gamma rays. Under reverse bias, an electric field extends across the intrinsic or depleted region. In this case, negative voltage is applied to the p-side and positive to the second one. Holes in the p-region are attracted from the junction towards the p contact and similarly for electrons and the n contact.
Scintillation Detector. Some EPDs use a scintillating crystal such as sodium iodide (NaI) or cesium iodide (CsI) with a photodiode or photomultiplier tube to measure photons released by radiation.
Characteristics of EPDs
The electronic personal dosimeter, EPD, is able to display a direct reading of the detected dose or dose rate in real time. Electronic dosimeters may be used as a supplemental dosimeter as well a primary dosimeter. The passive dosimeters and the electronic personal dosimeters are often used together to complement each other. To estimate effective doses, dosimeters must be worn on a position of the body representative of its exposure, typically between the waist and the neck, on the front of the torso, facing the radioactive source. Dosimeters are usually worn on the outside of clothing, around the chest or torso to represent dose to the “whole body”. Dosimeters may also be worn on the extremities or near the eye to measure equivalent dose to these tissues.
The dosimeter can be reset, usually after taking a reading for record purposes, and thereby re-used multiple times. The EPDs have a top mounted display to make them easy to read when they are clipped to your breast pocket. The digital display gives both dose and dose rate information usually in mSv and mSv/h. The EPD has a dose rate alarm, and a dose alarm. These alarms are programmable. Different alarms can be set for different activities.
For example:
dose rate alarm at 100 μSv/h,
dose alarm: 100 μSv.
If an alarm set point is reached, the relevant display flashes along with a red light, and quite a piercing noise is generated. You can clear the dose rate alarm by retreating to a lower radiation field, but you cannot clear the dose alarm until you get to a EPD reader. EPDs can also give a bleep for every 1 or 10 μSv they register. This gives you an audible indication of the radiation fields. Some EPDs have wireless communication capabilities. EPDs are capable of measuring a wide radiation dose range from routine (μSv) levels to emergency levels (hundreds mSv or units of Sieverts) with high precision, and may display the exposure rate as well as accumulated exposure values. Of the dosimeter technologies, electronic personal dosimeters are generally the most expensive, largest in size, and the most versatile.
DMC 3000 – Mirion Technologies Inc.
The DMC 3000 is an electronic radiation dosimeter, EPD, that provides dose and ambient dose rate readings for deep dose equivalent Hp(10). It is one of the most used EPDs on the market. It uses a Si chipdetector with gamma sensitivity of 180 cps/R/h. This electronic personal dosimeter has the following characteristics:
Energy response (X-ray and gamma) from 15 keV to 7 Mev.
Dose measurement display range: between 1 μSv and 10 Sv.
Rate measurement display range: between 10 μSv/hr and 10 Sv/h.
The device measures 3.3 x 1.9 x 0.7 inches and has options for being clipped to a pocket, belt, or lanyard. It is powered with rechargeable or AAA batteries with a battery life of up to 2,500 hours of continuous use. Audible and visual indicators signal a low battery condition. The device has a backlit, eight-digit LCD display; two-button navigation; and visual LED, audible, and vibrating alarm indicators. Calibration is expected to last 9 months under routine use and 2 years in storage. Data is stored in nonvolatile memory. The operating range for the dosimeter is from 14°F to 122°F and up to 90 percent relative humidity. It is drop tested to 1.5 meters. The DMC 3000 has optional external modules that expand the device’s detection and communication capabilities. These include a beta module that provides Hp(0,07) for beta radiation measurement; a neutron module that provides Hp(10) neutron radiation measurement; and a telemetry module that allows transmission of data to an external station.
See also: The Radiation Dosimeters for Response and Recovery Market Survey Report. National Urban Security Technology Laboratory. SAVER-T-MSR-4. <available from: https://www.dhs.gov/sites/default/files/publications/Radiation-Dosimeters-Response-Recovery-MSR_0616-508_0.pdf>.
Medical Dosimetry
Medical dosimetry is the calculation of absorbed dose and optimization of dose delivery in medical examinations and treatments. In general, radiation exposures from medical diagnostic examinations are low (especially in diagnostic uses). Doses may be also high (only for therapeutic uses), but in each case, they must be always justified by the benefits of accurate diagnosis of possible disease conditions or by benefits of accurate treatment. These doses include contributions from medical and dental diagnostic radiology (diagnostic X-rays), clinical nuclear medicine and radiation therapy. Medical dosimetry is often performed by a professional health physicist with specialized training in that field. In order to plan the delivery of radiation therapy, the radiation produced by the sources is usually characterized with percentage depth dose curves and dose profiles measured by a medical physicist.
The medical use of ionizing radiation remains a rapidly changing field. In any case, usefulness of ionizing radiation must be balanced with its hazards. Nowadays a compromise was found and most of uses of radiation are optimized. Today it is almost unbelievable that x-rays was, at one time, used to find the right pair of shoes (i.e. shoe-fitting fluoroscopy). Measurements made in recent years indicate that the doses to the feet were in the range 0.07 – 0.14 Gy for a 20 second exposure. This practice was halted when the risks of ionizing radiation were better understood.
Environmental dosimetry is used where it is likely that the environment will generate a significant radiation dose. As was written, radiation is all around us. In, around, and above the world we live in. It is a natural energy force that surrounds us. It is a part of our natural world that has been here since the birth of our planet. All living creatures, from the beginning of time, have been, and are still being, exposed to ionizing radiation. Ionizing radiation is generated through nuclear reactions, nuclear decay, by very high temperature, or via acceleration of charged particles in electromagnetic fields.
In general, there are two broad categories of radiation sources in the environment:
Natural Background Radiation. Natural background radiation includes radiation produced by the Sun, lightnings, primordial radioisotopes or supernova explosions etc.
Man-Made Sources of Radiation. Man-made sources include medical uses of radiation, residues from nuclear tests, industrial uses of radiation etc.
An example of environment dosimetry is radon monitoring. Radon is a radioactive gas generated by the decay of uranium, which is present in varying amounts in the earth’s crust. It is important to note that radon is a noble gas, whereas all its decay products are metals. The main mechanism for the entry of radon into the atmosphere is diffusion through the soil. Certain geographic areas, due to the underlying geology, continually generate radon which permeates its way to the earth’s surface. In some cases the dose can be significant in buildings where the gas can accumulate. Locations with higher radon background are well mapped in each country. In the open air, it ranges from 1 to 100 Bq/m3, even less (0.1 Bq/m3) above the ocean. In caves or aerated mines, or ill-aerated houses, its concentration climbs to 20–2,000 Bq/m3. In the outdoor atmosphere, there is also some advection caused by wind and changes in barometric pressure. A number of specialised dosimetry techniques are used to evaluate the dose that a building’s occupants may receive.
Example - Gamma Spectroscopy
Gamma Spectroscopy
As was written, the study and analysis of gamma ray spectra for scientific and technical use is called gamma spectroscopy, and gamma ray spectrometers are the instruments which observe and collect such data. A gamma ray spectrometer (GRS) is a sophisticated device for measuring the energy distribution of gamma radiation. For the measurement of gamma rays above several hundred keV, there are two detector categories of major importance, inorganic scintillators as NaI(Tl) and semiconductor detectors. In the previous articles, we described the gamma spectroscopy using scintillation detector, which consists of a suitable scintillator crystal, a photomultiplier tube, and a circuit for measuring the height of the pulses produced by the photomultiplier. The advantages of a scintillation counter are its efficiency (large size and high density) and the high precision and counting rates that are possible. Due to the high atomic number of iodine, a large number of all interactions will result in complete absorption of gamma-ray energy, so the photo fraction will be high.
HPGe detector with LN2 cryostat Source: canberra.com
But if a perfect energy resolution is required, we have to use germanium-based detector, such as the HPGe detector. Germanium-based semiconductor detectors are most commonly used where a very good energy resolution is required, especially for gamma spectroscopy, as well as x-ray spectroscopy. In gamma spectroscopy, germanium is preferred due to its atomic number being much higher than silicon and which increases the probability of gamma ray interaction. Moreover, germanium has lower average energy necessary to create an electron-hole pair, which is 3.6 eV for silicon and 2.9 eV for germanium. This also provides the latter a better resolution in energy. The FWHM (full width at half maximum) for germanium detectors is a function of energy. For a 1.3 MeV photon, the FWHM is 2.1 keV, which is very low.
Radiation Dose Measuring and Monitoring
In previous chapters, we described the equivalent dose and the effective dose. But these doses are not directly measurable. For this purpose, the ICRP has introduced and defined a set of operational quantities, which can be measured and which are intended to provide a reasonable estimate for the protection quantities. These quantities aim to provide a conservative estimate for the value of the protection quantities related to an exposure avoiding both underestimation and too much overestimation.
Numerical links between these quantities is represented by conversion coefficients, which are defined for a reference person. It is very important that an internationally agreed set of conversion coefficients is available for general use in radiological protection practice for occupational exposures and exposures of the public. For the calculation of conversion coefficients for external exposure, computational phantoms are used for dose assessment in various radiation fields. For the calculation of dose coefficients from intakes of radionuclides, biokinetic models for radionuclides, reference physiological data, and computational phantoms are used.
A set of evaluated data of conversion coefficients for protection, and operational quantities for external exposure to mono-energetic photon, neutron, and electron radiation under specific irradiation conditions is published in reports (ICRP, 1996b, ICRU, 1997).
In general, the ICRP defines operational quantities for area and individual monitoring of external exposures. The operational quantities for area monitoring are:
Ambient dose equivalent, H*(10). The ambient dose equivalent is an operational quantity for area monitoring of strongly penetrating radiation.
Directional dose equivalent, H’ (d,Ω). The directional dose equivalent is an operational quantity for area monitoring of weakly penetrating radiation.
Personal dose equivalent, Hp(0.07). The Hp(0.07) dose equivalent is an operational quantity for individual monitoring for the assessment of the dose to the skin and to the hands and feet.
Personal dose equivalent, Hp(10). The Hp(10) dose equivalent is an operational quantity for individual monitoring for the assessment of effective dose.
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Dose limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Sievert – Unit of Equivalent Dose
In radiation protection, the sievert is a derived unit of equivalent dose and effective dose. The sievert represents the equivalent biological effect of the deposit of a joule of gamma rays energy in a kilogram of human tissue. Unit of sievert is of importance in radiation protection and was named after the Swedish scientist Rolf Sievert, who did a lot of the early work on radiation dosimetry in radiation therapy.
As was written, the sievert is used for radiation dose quantities such as equivalent dose and effective dose. Equivalent dose (symbol HT) is a dose quantity calculated for individual organs (index T – tissue). Equivalent dose is based on the absorbed dose to an organ, adjusted to account for the effectiveness of the type of radiation. Equivalent dose is given the symbol HT. The SI unit of HT is the sievert (Sv) or but rem (roentgen equivalent man) is still commonly used (1 Sv = 100 rem).
Examples of Doses in Sieverts
We must note that radiation is all around us. In, around, and above the world we live in. It is a natural energy force that surrounds us. It is a part of our natural world that has been here since the birth of our planet. In the following points we try to express enormous ranges of radiation exposure, which can be obtained from various sources.
0.05 µSv – Sleeping next to someone
0.09 µSv – Living within 30 miles of a nuclear power plant for a year
0.1 µSv – Eating one banana
0.3 µSv – Living within 50 miles of a coal power plant for a year
10 µSv – Average daily dose received from natural background
20 µSv – Chest X-ray
40 µSv – A 5-hour airplane flight
600 µSv – mammogram
1 000 µSv – Dose limit for individual members of the public, total effective dose per annum
3 650 µSv – Average yearly dose received from natural background
5 800 µSv – Chest CT scan
10 000 µSv – Average yearly dose received from natural background in Ramsar, Iran
20 000 µSv – single full-body CT scan
175 000 µSv – Annual dose from natural radiation on a monazite beach near Guarapari, Brazil.
5 000 000 µSv – Dose that kills a human with a 50% risk within 30 days (LD50/30), if the dose is received over a very short duration.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Nuclear Engineering
We hope, this article, Radiation Dosimetry, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
In order to detect invisible light, some detectors must be used. In their basic principles of operation, most detectors of ionizing radiation follow similar characteristics. Detection of Invisible Radiation
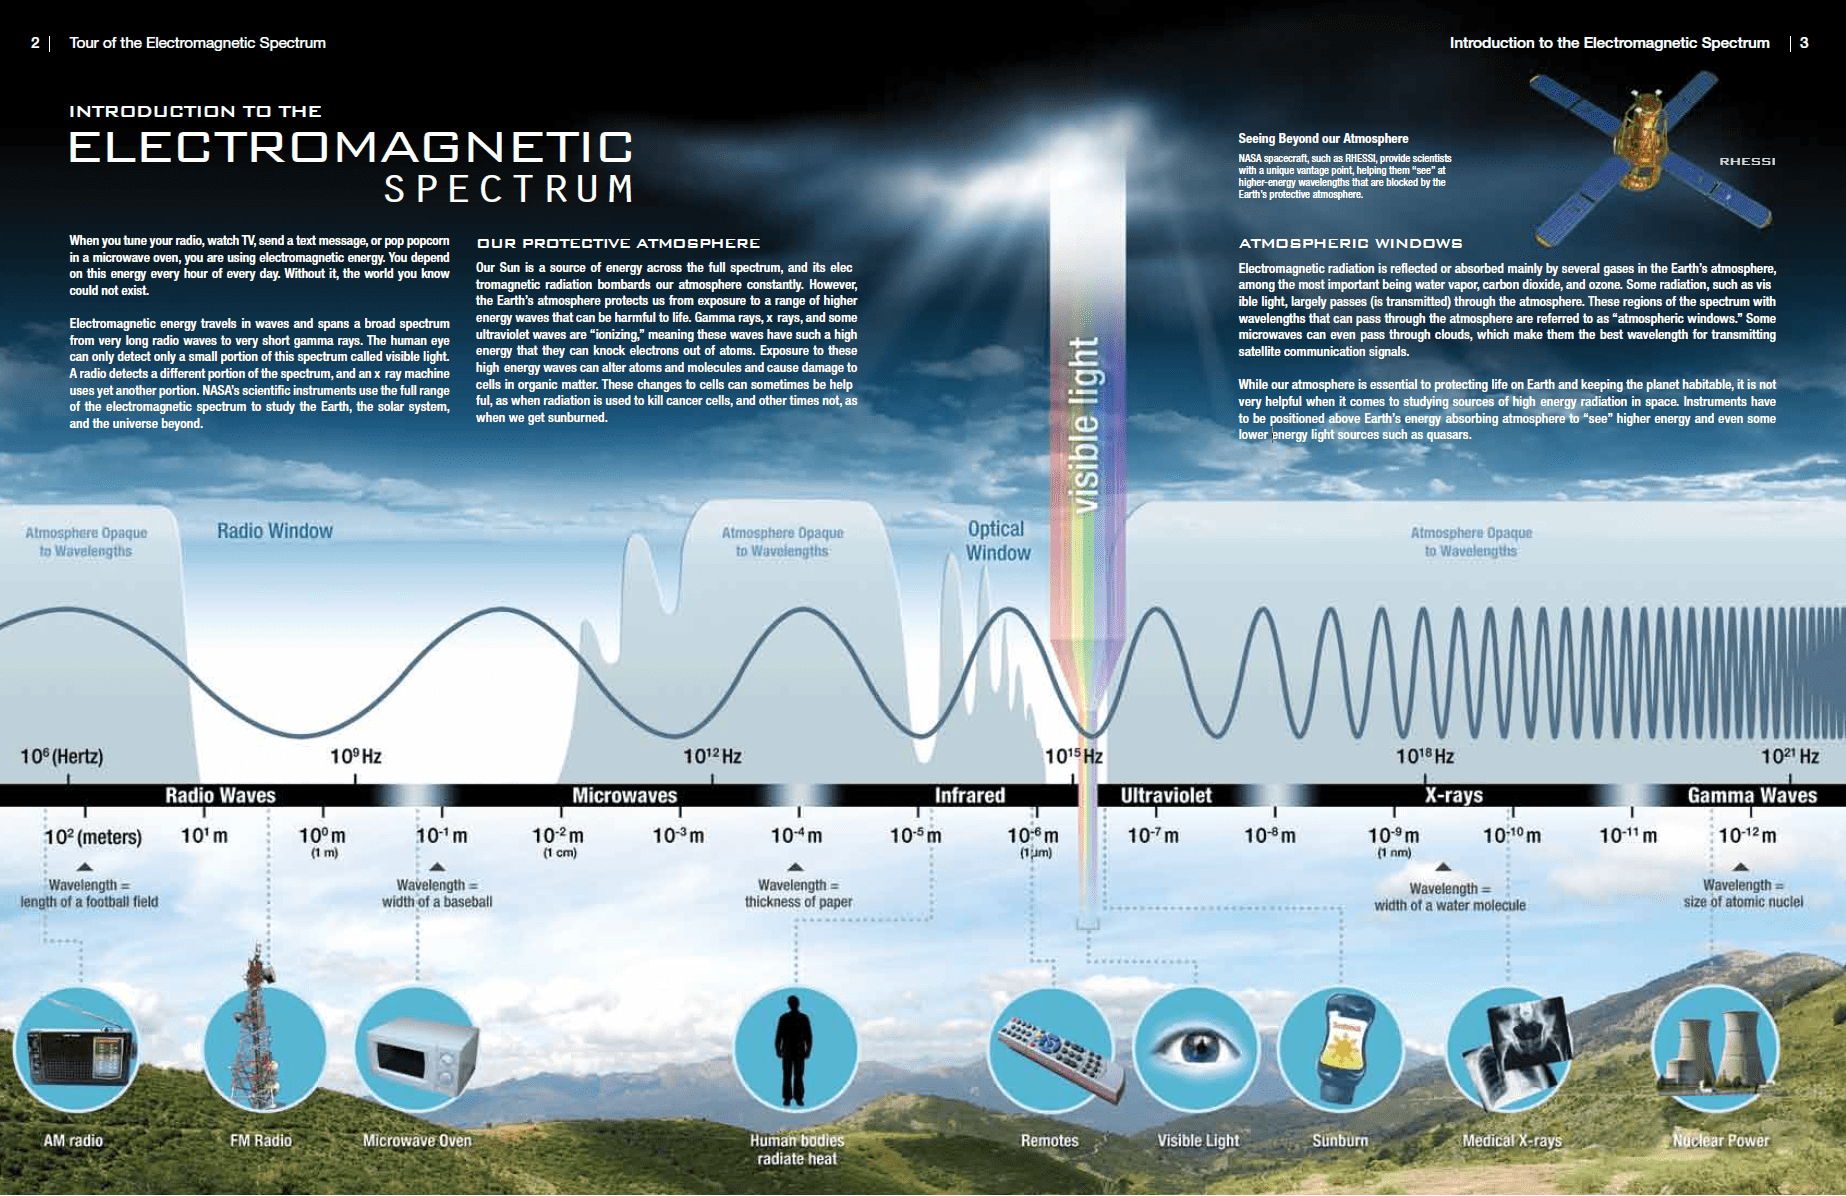
All electromagnetic radiation except visible light (a very narrow band) is invisible. Invisible radiation includes radio waves, infrared, UV, microwaves, and gamma radiation. In addition, alpha and beta radiation as well as “”cathode rays” – all of which are streams of particles – are invisible.
Noteworthy neither invisible radiation is completely invisible to the human eye. A related topic is that of cosmic-ray visual phenomena, in which astronauts can see flashes of light, which are presumably due to individual cosmic-ray particles interacting with their eyes. Researchers believe that these light flashes perceived specifically by astronauts in space are due to cosmic rays (high-energy charged particles from beyond the Earth’s atmosphere), though the exact mechanism is unknown.
Detection of Invisible Radiation
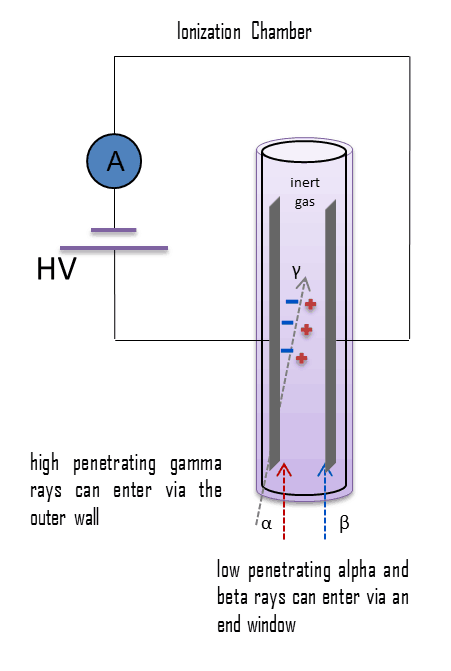
Detectors of ionizing radiation consist of two parts that are usually connected. The first part consists of a sensitive material, consisting of a compound that experiences changes when exposed to radiation. The other component is a device that converts these changes into measurable signals.
In their basic principles of operation, most detectors of ionizing radiation follow similar characteristics. Detectors of ionizing radiation consist of two parts that are usually connected. The first part consists of a sensitive material, consisting of a compound that experiences changes when exposed to radiation. The other component is a device that converts these changes into measurable signals. All detectors require that radiation must deposit some of its energy in sensitive material that forms part of the instrument. The radiation enters the detector, interacts with atoms of the detector material and deposits some energy to sensitive material. Each event may generate a signal, which can be a pulse, hole, light signal, ion pairs in a gas, and many others. The main task is to generate sufficient signal, amplify it and to record it.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Visible and Invisible Radiation
We hope, this article, Detection of Invisible Radiation, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Invisible radiation includes radio waves, infrared, UV, microwaves, and gamma radiation. In addition, alpha and beta radiation as well as “”cathode rays” – all of which are streams of particles – are invisible.
Source: Tour of the Electromagnetic Spectrum www.nasa.gov
In general, electromagnetic radiation may be divided into a visible and invisible portion of electromagnetic spectrum. Light is electromagnetic radiation within a certain portion of the electromagnetic spectrum. At the lower end of the visible light spectrum, electromagnetic radiation becomes invisible to humans (infrared) because its photons no longer have enough individual energy to cause a lasting molecular change (a change in conformation) in the visual molecule retinal in the human retina, which change triggers the sensation of vision.
Invisible Radiation
All electromagnetic radiation except visible light (a very narrow band) is invisible. Invisible radiation includes radio waves, infrared, UV, microwaves, and gamma radiation. In addition, alpha and beta radiation as well as “”cathode rays” – all of which are streams of particles – are invisible.
Noteworthy neither invisible radiation is completely invisible to the human eye. A related topic is that of cosmic-ray visual phenomena, in which astronauts can see flashes of light, which are presumably due to individual cosmic-ray particles interacting with their eyes. Researchers believe that these light flashes perceived specifically by astronauts in space are due to cosmic rays (high-energy charged particles from beyond the Earth’s atmosphere), though the exact mechanism is unknown.
The danger of ionizing radiation lies in the fact that the radiation is invisible and not directly detectable by human senses. People can neither see nor feel radiation, yet it deposits energy to the molecules of material. The energy is transferred in small quantities for each interaction between the radiation and a molecule and there are usually many types of interactions. Therefore, the only way you can detect and measure radiation is to use instruments (detectors of ionizing radiation).
Detection of Invisible Radiation
Detectors of ionizing radiation consist of two parts that are usually connected. The first part consists of a sensitive material, consisting of a compound that experiences changes when exposed to radiation. The other component is a device that converts these changes into measurable signals.
In their basic principles of operation, most detectors of ionizing radiation follow similar characteristics. Detectors of ionizing radiation consist of two parts that are usually connected. The first part consists of a sensitive material, consisting of a compound that experiences changes when exposed to radiation. The other component is a device that converts these changes into measurable signals. All detectors require that radiation must deposit some of its energy in sensitive material that forms part of the instrument. The radiation enters the detector, interacts with atoms of the detector material and deposits some energy to sensitive material. Each event may generate a signal, which can be a pulse, hole, light signal, ion pairs in a gas, and many others. The main task is to generate sufficient signal, amplify it and to record it.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Visible and Invisible Radiation
We hope, this article, Invisible Radiation, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
The danger of ionizing radiation lies in the fact that the radiation is invisible and not directly detectable by human senses. People can neither see nor feel radiation, yet it deposits energy to the molecules of material. Radiation Dosimetry
Executive Summary
Radiation is all around us. We are continually exposed to natural background radiation and it seems to be without any problem. Yes, high doses of ionizing radiation is harmful and potentially lethal to living beings, but these doses must be really high. Moreover, what is not harmful in high doses? Even high amount of water can be lethal to living beings.
The truth about low-dose radiation health effects still needs to be found. It is not exactly known, whether these low doses of radiation are detrimental or beneficial (and where is the threshold). There are studies, that claim, that small doses of radiation given at a low dose rate stimulate the defense mechanisms. Moreover, ionizing radiation can have health benefits in medicine, for example, in diagnostics where X-rays are used to produce pictures of the inside of the body. We do not claim, everything is OK. It also depends on the type of radiation and tissue, which was exposed.
But finally, if you compare risks, which arise from existence of radiation, natural or artificial, with risks, which arise from everyday life, then you must conclude that fear of radiation is irrational. Humans are often inconsistent in our treatment of perceived risks. Even though two situations may have similar risks, people will find one situation permissible and another unjustifiably dangerous.
The problem of ionizing radiation lies in the fact that the radiation is invisible and not directly detectable by human senses. People can neither see nor feel radiation, and therefore they feel fear of this invisible threat.
Ionizing radiation – hazard symbol
How Dangerous is Radiation
Radiation is all around us. In, around, and above the world we live in. It is a natural energy force that surrounds us. It is a part of our natural world that has been here since the birth of our planet. All living creatures, from the beginning of time, have been, and are still being, exposed to ionizing radiation.
For example, potassium-40 is one of isotopes which contributes to internal exposure of human. Traces of potassium-40 are found in all potassium, and it is the most common radioisotope in the human body. Higher amounts can be also found in bananas. Does it mean, eating bananas must be dangerous? Of course not.
Explanation - Banana Equivalent Dose
In all cases, intensity of radiation matters. Banana equivalent dose is intended as a general educational example to compare a dose of radioactivity to the dose one is exposed to by eating one average-sized banana. One BED is often correlated to 10-7 Sievert (0.1 µSv). The radiation exposure from consuming a banana is approximately 1% of the average daily exposure to radiation, which is 100 banana equivalent doses (BED). A chest CT scan delivers 58,000 BED (5.8 mSv). A lethal dose, the dose that kills a human with a 50% risk within 30 days (LD50/30) of radiation, is approximately 50,000,000 BED (5000 mSv). However, in practice, this dose is not cumulative, as the principal radioactive component is excreted to maintain metabolic equilibrium. Moreover, there is also a problem with the collective dose.
The BED is only meant to inform the public about the existence of very low levels of natural radioactivity within a natural food and is not a formally adopted dose measurement.
Whether the source of radiation is natural or man-made, whether it is a large dose of radiation or a small dose, there will be some biological effects. In general, ionizing radiation is harmful and potentially lethal to living beings but can have health benefits in medicine, for example, in radiation therapy for the treatment of cancer and thyrotoxicosis.
But where is the threshold between positive and negative effects of radiation?
What does danger mean?
In the following thoughts, we try to summarize facts and hypothesis, which can help you understand the problem. It is all about the risks arising from exposure to ionizing radiation and about the consistency in all risks of everyday life. But first we have to summarize key facts about ionizing radiation.
Intensity of Radiation – Dose and Dose Rate
Principles of Radiation Protection – Time, Distance, Shielding
Intensity of ionizing radiation is a key factor, which determines health effects from being exposed to any radiation. It is similar as being exposed to heat radiation from a fire (in fact, it is also transferred by photons). If you are too close to a fire, the intensity of thermal radiation is high and you can get burned. If you are at the right distance, you can withstand there without any problems and moreover it is comfortable. If you are too far from heat source, the insufficiency of heat can also hurt you. This analogy, in a certain sense, can be applied to radiation also from ionizing radiation sources.
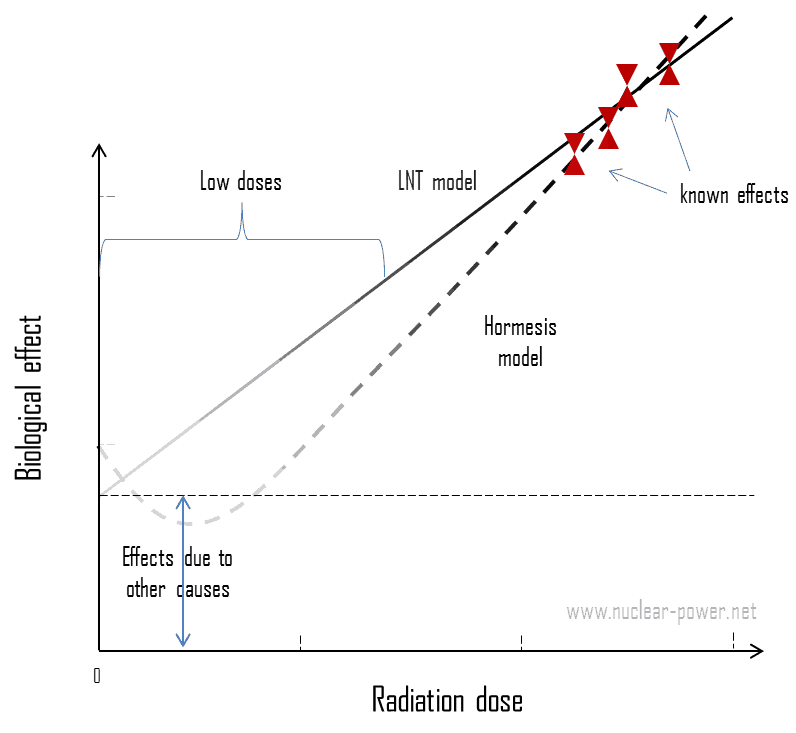
In short, to get burned (deterministic effects and demonstrable stochastic effects) by ionizing radiation, you must be exposed to really high amount of radiation. But almost everytime, we are talking about so called low doses. As was written, today the protection system is based on the LNT-hypothesis, which is a conservative model used in radiation protection to estimate the health effects from small radiation doses. This model is excellent for setting up a protection system for all use of ionizing radiation. This model assumes, that there is no threshold point and risk increases linearly with a dose, i.e. the LNT model implies that there is no safe dose of ionizing radiation. If this linear model is correct, then natural background radiation is the most hazardous source of radiation to general public health, followed by medical imaging as a close second. It must be added, the research during the last two decades is very interesting and show that small doses of radiation given at a low dose rate stimulate the defense mechanisms. Therefore the LNT model is not universally accepted with some proposing an adaptive dose–response relationship where low doses are protective and high doses are detrimental. Many studies have contradicted the LNT model and many of these have shown adaptive response to low dose radiation resulting in reduced mutations and cancers. On the other hand, it is very important, to what type of radiation is a person exposed.
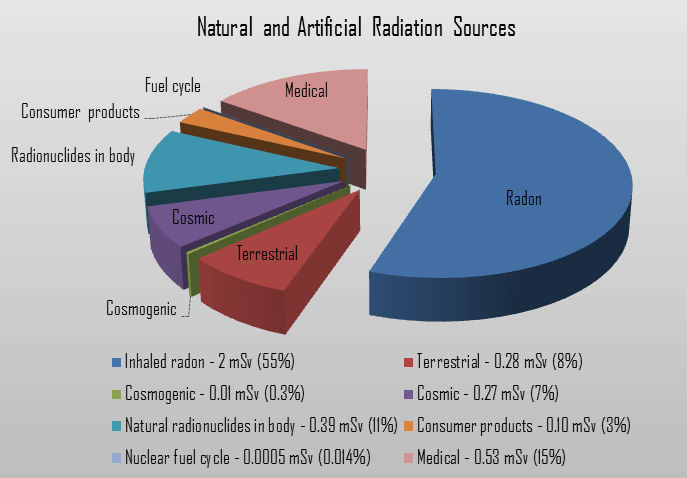
Natural Background Radiation
Natural background radiation is ionizing radiation, that originates from a variety of natural sources. All living creatures, from the beginning of time, have been, and are still being, exposed to ionizing radiation. This radiation is not associated with any human activity. There are radioactive isotopes in our bodies, houses, air, water and in the soil. We all are also exposed to radiation from outer space.
Sources of Natural Background Radiation
We divide all these natural radiation sources into three groups:
Alternative assumptions for the extrapolation of the cancer risk vs. radiation dose to low-dose levels, given a known risk at a high dose: LNT model, and hormesis model.
You can not go through life without radiation. The danger of ionizing radiation lies in the fact that the radiation is invisible and not directly detectable by human senses. People can neither see nor feel radiation, yet it deposits energy to the molecules of the body.
But don’t worry, the doses from background radiation are usually very small (except radon exposure). Low dose here means additional small doses comparable to the normal background radiation (10 µSv = average daily dose received from natural background). The problem is that, at very low doses, it is practically impossible to correlate any irradiation with certain biological effects. This is because the baseline cancer rate is already very high and the risk of developing cancer fluctuates 40% because of individual life style and environmental effects, obscuring the subtle effects of low-level radiation.
Intensity - Acute and Chronic Doses
Biological effects of radiation and their consequences depends strongly on the level of dose rate obtained. Dose rate is a measure of radiation dose intensity (or strength). Low-level doses are common for everyday life. In the following points there are a few examples of radiation exposure, which can be obtained from various sources.
05 µSv – Sleeping next to someone
09 µSv – Living within 30 miles of a nuclear power plant for a year
1 µSv – Eating one banana
3 µSv – Living within 50 miles of a coal power plant for a year
10 µSv – Average daily dose received from natural background
20 µSv – Chest X-ray
From biological consequences point of view, it is very important to distinguish between doses received over short and extended periods. Therefore, biological effects of radiation are typically divided into two categories.
Acute Doses. An “acute dose” (short-term high-level dose) is one that occurs over a short and finite period of time, i.e., within a day.
Chronic Doses. A “chronic dose” (long-term low-level dose) is a dose that continues for an extended period of time, i.e., weeks and months, so that it is better described by a dose rate.
High doses tend to kill cells, while low doses tend to damage or change them. High doses can cause visually dramatic radiation burns, and/or rapid fatality through acute radiation syndrome. Acute doses below 250 mGy are unlikely to have any observable effects. Acute doses of about 3 to 5 Gy have a 50% chance of killing a person some weeks after the exposure, if a person receives no medical treatment.
Low doses spread out over long periods of time don’t cause an immediate problem to any body organ. The effects of low doses of radiation occur at the level of the cell, and the results may not be observed for many years. Moreover, some studies demonstrate, most of human tissues exhibit a more pronounced tolerance to the effects of low-LET radiation in case of a prolonged exposure compared to a one-time exposure to a similar dose.
In radiation protection, most adverse health effects of radiation exposure are usually divided into two broad classes:
Deterministic effects are threshold health effects, that are related directly to the absorbed radiation dose and the severity of the effect increases as the dose increases.
Stochastic effects occur by chance, generally occurring without a threshold level of dose. Probability of occurrence of stochastic effects is proportional to the dose but the severity of the effect is independent of the dose received.
Deterministic Effects
Deterministic effects (or non-stochastic health effects) are health effects, that are related directly to the absorbed radiation dose and the severity of the effect increases as the dose increases. Deterministic effects have a threshold below which no detectable clinical effects do occur. The threshold may be very low (of the order of magnitude of 0.1 Gy or higher) and may vary from person to person. For doses between 0.25 Gy and 0.5 Gy slight blood changes may be detected by medical evaluations and for doses between 0.5 Gy and 1.5 Gy blood changes will be noted and symptoms of nausea, fatigue, vomiting occur.
Once the threshold has been exceeded, the severity of an effect increases with dose. The reason for the presence of this threshold dose is that radiation damage (serious malfunction or death) of a critical population of cells (high doses tend to kill cells) in a given tissue needs to be sustained before injury is expressed in a clinically relevant form. Therefore, deterministic effects are also termed tissue reaction. They are also called non-stochastic effects to contrast with chance-like stochastic effects (e.g. cancer induction).
Deterministic effects are not necessarily more or less serious than stochastic effects. High doses can cause visually dramatic radiation burns, and/or rapid fatality through acute radiation syndrome. Acute doses below 250 mGy are unlikely to have any observable effects. Acute doses of about 3 to 5 Gy have a 50% chance of killing a person some weeks after the exposure, if a person receives no medical treatment. Deterministic effects can ultimately lead to a temporary nuisance or also to a fatality. Examples of deterministic effects:
Examples of deterministic effects are:
Acute radiation syndrome, by acute whole-body radiation
Radiation burns, from radiation to a particular body surface
Radiation-induced thyroiditis, a potential side effect from radiation treatment against hyperthyroidism
Chronic radiation syndrome, from long-term radiation.
Radiation-induced lung injury, from for example radiation therapy to the lungs
Stochastic Effects
Stochastic effectsof ionizing radiation occur by chance, generally occurring without a threshold level of dose. Probability of occurrence of stochastic effects is proportional to the dose but the severity of the effect is independent of the dose received. The biological effects of radiation on people can be grouped into somatic and hereditary effects. Somatic effects are those suffered by the exposed person. Hereditary effects are those suffered by the offspring of the individual exposed. Cancer risk is usually mentioned as the main stochastic effect of ionizing radiation, but also hereditary disorders are stochastic effects.
According to ICRP:
(83) On the basis of these calculations the Commission proposes nominal probability coefficients for detriment-adjusted cancer risk as 5.5 x 10⁻² Sv-1 for the whole population and 4.1 x 10⁻² Sv-1 for adult workers. For heritable effects, the detriment-adjusted nominal risk in the whole population is estimated as 0.2 x 10⁻² Sv-1 and in adult workers as 0.1 x 10⁻² Sv-1 .
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
The SI unit for effective dose, the sievert, represents the equivalent biological effect of the deposit of a joule of gamma rays energy in a kilogram of human tissue. As a result, one sievert represents a 5.5% chance of developing cancer. Note that, the effective dose is not intended as a measure of deterministic health effects, which is the severity of acute tissue damage that is certain to happen, that is measured by the quantity absorbed dose.
Biological Effects and Dose Limits
In radiation protection, dose limits are set to limit stochastic effects to an acceptable level, and to prevent deterministic effects completely. Note that, stochastic effects are those arising from chance: the greater the dose, the more likely the effect. Deterministic effects are those which normally have a threshold: above this, the severity of the effect increases with the dose. Dose limits are a fundamental component of radiation protection, and breaching these limits is against radiation regulation in most countries. Note that, the dose limits described in this article apply to routine operations. They do not apply to an emergency situation when human life is endangered. They do not apply in emergency exposure situations where an individual is attempting to prevent a catastrophic situation.
The limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Controversy of LNT Model
As was written previously (LNT model), today the protection system is based on the LNT-hypothesis, which is a conservative model used in radiation protection to estimate the health effects from small radiation doses. This model is excellent for setting up a protection system for all use of ionizing radiation. In comparison to the hormesis model, the LNT model assumes, that there is no threshold point and risk increases linearly with a dose, i.e. the LNT model implies that there is no safe dose of ionizing radiation. If this linear model is correct, then natural background radiation is the most hazardous source of radiation to general public health, followed by medical imaging as a close second.
The LNT model is primarily based on the life span study (LSS) of atomic bomb survivors in Japan. However, while this pattern is undisputed at high doses, this linear extrapolation of risk to low doses is challenged by many recent experiments involving cell mechanisms and there is also high uncertainty involved in estimating risk using only epidemiological studies. The problem is that, at very low doses, it is practically impossible to correlate any irradiation with certain biological effects. This is because the baseline cancer rate is already very high and the risk of developing cancer fluctuates 40% because of individual life style and environmental effects, obscuring the subtle effects of low-level radiation. Government and regulatory bodies assume a LNT model instead of a threshold or hormesis not because it is the more scientifically convincing, but because it is the more conservative estimate.
In case of low doses, its conservativeness (linearity) has enormous consequences and the model is sometimes wrongly (perhaps intentionally) used to quantify the cancerous effect of collective doses of low-level radioactive contamination. A linear dose-effect curve makes it possible to use collective doses to calculate the detrimental effects to an irradiated population. It is also argued that LNT model had caused an irrational fear of radiation, since every microsievert can be converted to the probability of cancer induction, however small this probability is. For example, if ten million people receives an effective dose of 0.1 µSv (an equivalent of eating one banana), then the collective dose will be S = 1 Sv. Does it mean there is 5.5% chance of developing cancer for one person due to eating banana? Note that, for high doses one sievert represents a 5.5% chance of developing cancer.
Problem of this model is that it neglects a number of defence biological processes that may be crucial at low doses. The research during the last two decades is very interesting and show that small doses of radiation given at a low dose rate stimulate the defense mechanisms. Therefore the LNT model is not universally accepted with some proposing an adaptive dose–response relationship where low doses are protective and high doses are detrimental. Many studies have contradicted the LNT model and many of these have shown adaptive response to low dose radiation resulting in reduced mutations and cancers.
Type of Radiation – High-LET x Low-LET
Source: ICRP Publ. 103: The 2007 Recommendations of the International Commission on Radiological Protection
This section is about the fact, that there are several types of ionizing radiation and each type of radiation interacts with matter in a different way. When discussing the intensity of radiation, we have to take into account to which type of radiation are you exposed. For example, alpha radiation tend to travel only a short distance and do not penetrate very far into tissue if at all. Therefore, alpha radiation is sometimes treated as non-hazardous, since it cannot penetrate surface layers of human skin. This is naturally true, but this is not valid for internal exposure by alpha radionuclides. When inhaled or ingested, alpha radiation is much more dangerous than other types of radiation. Note that, the radiation weighting factor for alpha radiation is equal to 20. It was discovered, biological effects of any radiation increases with the linear energy transfer (LET). In short, the biological damage from high-LET radiation (alpha particles, protons or neutrons) is much greater than that from low-LET radiation (gamma rays).
Ionizing radiation is categorized by the nature of the particles or electromagnetic waves that create the ionizing effect. These particles/waves have different ionization mechanisms, and may be grouped as:
Directly ionizing. Charged particles (atomic nuclei, electrons, positrons, protons, muons, etc.) can ionize atoms directly by fundamental interaction through the Coulomb force if it carries sufficient kinetic energy. These particles must be moving at relativistic speeds to reach the required kinetic energy. Even photons (gamma rays and X-rays) can ionize atoms directly (despite they are electrically neutral) through the Photoelectric effect and the Compton effect, but secondary (indirect) ionization is much more significant.
Indirectly ionizing. Indirect ionizing radiation is electrically neutral particles and therefore does not interact strongly with matter. The bulk of the ionization effects are due to secondary ionizations.
As was written, it is crucial, whether we are exposed to radiation from external sources or from internal sources. This is similar as for another dangerous substances. Internal exposure is more dangerous than external exposure, since we are carrying the source of radiation inside our bodies and we cannot use any of radiation protection principles (time, distance, shielding). The intake of radioactive material can occur through various pathways such as ingestion of radioactive contamination in food or liquids, inhalation of radioactive gases, or through intact or wounded skin. On this place, we have to distinguish between radiation and contamination. Radioactive contamination consist of radioactive material, that generate ionizing radiation. It is the source of radiation, not radiation itself. Anytime that radioactive material is not in a sealed radioactive source container and might be spread onto other objects, radioactive contamination is a possibility. For example, radioiodine, iodine-131, is an important radioisotope of iodine. Radioiodine plays a major role as a radioactive isotope present in nuclear fission products, and it is a major contributor to the health hazards when released into the atmosphere during an accident. Iodine-131 has a half-life of 8.02 days. The target tissue for radioiodine exposure is the thyroid gland. The external beta and gamma dose from radioiodine present in the air is quite negligible when compared to the committed dose to the thyroid that would result from breathing this air.
Internal Dose Uptake
If the source of radiation is inside our body, we say, it is internal exposure. The intake of radioactive material can occur through various pathways such as ingestion of radioactive contamination in food or liquids, inhalation of radioactive gases, or through intact or wounded skin. Most radionuclides will give you much more radiation dose if they can somehow enter your body, than they would if they remained outside. For internal doses, we first should distinguish between intake and uptake. Intake means what a person takes in. Uptake means what a person keeps.
When a radioactive compound enters the body, the activity will decrease with time, due both to radioactive decay and to biological clearance. The decrease varies from one radioactive compound to another. For this purpose, the biological half-life is defined in radiation protection.
The biological half-life is the time taken for the amount of a particular element in the body to decrease to half of its initial value due to elimination by biological processes alone, when the rate of removal is roughly exponential. The biological half-life depends on the rate at which the body normally uses a particular compound of an element. Radioactive isotopes that were ingested or taken in through other pathways will gradually be removed from the body via bowels, kidneys, respiration and perspiration. This means that a radioactive substance can be expelled before it has had the chance to decay.
As a result, the biological half-life significantly influences the effective half-life and the overall dose from internal contamination. If a radioactive compound with radioactive half-life (t1/2) is cleared from the body with a biological half-life tb, the effective half-life (te) is given by the expression:
As can be seen, the biological mechanisms always decreases the overall dose from internal contamination. Moreover, if t1/2 is large in comparison to tb, the effective half-life is approximately the same as tb.
For example, tritium has the biological half-life about 10 days, while the radioactive half-life is about 12 years. On the other hand, radionuclides with very short radioactive half-lives have also very short effective half-lives. These radionuclides will deliver, for all practical purposes, the total radiation dose within the first few days or weeks after intake.
For tritium, the annual limit intake (ALI) is 1 x 10⁹ Bq. If you take in 1 x 10⁹ Bq of tritium, you will receive a whole-body dose of 20 mSv. The committed effective dose, E(t), is therefore 20 mSv. It does not depend whether a person intakes this amount of activity in a short time or in a long time. In every case, this person gets the same whole-body dose of 20 mSv.
Contamination versus Radiation
Radioactive contamination consist of radioactive material, that generate ionizing radiation. It is the source of radiation, not radiation itself. Anytime that radioactive material is not in a sealed radioactive source container and might be spread onto other objects, radioactive contamination is a possibility. Radioactive contamination may be characterized by following points:
Radioactive contamination consist of radioactive material (contaminants), that may be solid, liquid or gaseous. Large contaminants can be even visible, but you cannot see radiation produced.
When released, contaminants can be spread by air, water or just by mechanical contact.
We cannot shield contamination.
We can mitigate contamination by protecting integrity of barriers (source container, fuel cladding, reactor vessel, containment building)
Since contaminants interact chemically, they may be contained within objects such as the human body.
We can rid of contamination by many mechanical, chemical (decontaminate surfaces), or biological processes (biological half-life).
It is of the highest importance, which material is the radioactive contaminant (half-life, mode of decay, energy).
Ionizing radiation is formed by high-energy particles (photons, electrons, etc.), that can penetrate matter and ionize (to form ion by losing electrons) target atoms to form ions. Radiation exposure is the consequence of the presence nearby the source of radiation. Radiation exposure as a quantity is defined as a measure of the ionization of material due to ionizing radiation. The danger of ionizing radiation lies in the fact that the radiation is invisible and not directly detectable by human senses. People can neither see nor feel radiation, yet it deposits energy to the molecules of the body. The energy is transferred in small quantities for each interaction between radiation and a molecule and there are usually many such interactions. Unlike radioactive contamination, radiation may be characterized by following points:
Radiation consist consist of high-energy particles that can penetrate matter and ionize (to form ion by losing electrons) target atoms. Radiation is invisible, and not directly detectable by human senses. It must be noted, beta radiation is indirectly visible due to cherenkov radiation.
Unlike contamination, radiation cannot be spread by any medium. It travels through materials until it loses its energy. We can shield radiation (e.g. by standing around the corner).
Exposure to ionizing does not necessary mean, that the object becomes radioactive (except very rare neutron radiation).
Radiation can penetrate barriers, but sufficiently thick barrier can minimize all effects.
Unlike contaminants, radiation cannot interact chemically with matter and cannot be bound inside body.
It is not important, which material is the source of certain radiation. Only type of radiation and energy matters.
Airborne Contamination
Airborne contamination is of particular importance in nuclear power plants, where it must be monitored. Contaminants can become airborne especially during reactor top head remove, reactor refueling, and during manipulations within spent fuel pool. The air can be contaminated with radioactive isotopes especially in particulate form, which poses a particular inhalation hazard. This contamination consists of various fission and activation products that enter the air in gaseous, vapour or particulate form. There are four types of airborne contamination in nuclear power plants, namely:
Particulates. Particulate activity is an internal hazard, because it can be inhaled. Transportable particulate material taken into the respiratory system will enter the blood stream and be carried to all parts of the body. Non-transportable particulates will stay in the lungs with a certain biological half-life. For example, Sr-90, Ra-226 and Pu-239 are radionuclides known as bone-seeking radionuclides. These radionuclides have long biological half-lives and are serious internal hazards. Once deposited in bone, they remain there essentially unchanged in amount during the lifetime of the individual. The continued action of the emitted alpha particles can cause significant injury: over many years they deposit all their energy in a tiny volume of tissue, because the range of the alpha particles is very short.
Noble gases. Radioactive noble gases, such as xenon-133, xenon-135 and krypton-85 are present in reactor coolant especially when fuel leakages are present. As they appear in coolant, they become airborne and they can be inhaled. They are exhaled right after they are inhaled, because the body does not react chemically with them. If workers are working in a noble gas cloud, the external dose they will receive is about 1000 times greater than the internal dose. Because of this, we are only concerned about the external beta and gamma dose rates.
Radioiodine. Radioiodine, iodine-131, is an important radioisotope of iodine. Radioiodine plays a major role as a radioactive isotope present in nuclear fission products, and it is a major contributor to the health hazards when released into the atmosphere during an accident. Iodine-131 has a half-life of 8.02 days. The target tissue for radioiodine exposure is the thyroid gland. The external beta and gamma dose from radioiodine present in the air is quite negligible when compared to the committed dose to the thyroid that would result from breathing this air. The biological half-life for iodine inside the human body is about 80 days (according to ICRP). Iodine in food is absorbed by the body and preferentially concentrated in the thyroid where it is needed for the functioning of that gland. When 131I is present in high levels in the environment from radioactive fallout, it can be absorbed through contaminated food, and will also accumulate in the thyroid. 131I decays with a half-life of 8.02 days with beta particle and gamma emissions. As it decays, it may cause damage to the thyroid. The primary risk from exposure to high levels of 131I is the chance occurrence of radiogenic thyroid cancer in later life. For 131I, ICRP has calculated that if you inhale 1 x 10⁶ Bq, you will receive a thyroid dose of HT = 400 mSv (and weighted whole-body dose of 20 mSv).
Tritium.Tritium is a byproduct in nuclear reactors. Most important source (due to releases of tritiated water) of tritium in nuclear power plants stems from the boric acid, which is commonly used as a chemical shim to compensate an excess of initial reactivity. Note that, tritium emits low-energy beta particles with a short range in body tissues and, therefore, poses a risk to health as a result of internal exposure only following ingestion in drinking water or food, or inhalation or absorption through the skin. The tritium taken into the body is uniformly distributed among all soft tissues. According to the ICRP, a biological half-time of tritium is 10 days for HTO and 40 days for OBT (organically bound tritium) formed from HTO in the body of adults. As a result, for an intake of 1 x 10⁹ Bq of tritium (HTO), an individual will get a whole-body dose of 20 mSv (equal to the intake of 1 x 10⁶ Bq of 131I). While for PWRs tritium poses a minor risk to health, for heavy water reactors, it contributes significantly to collective dose of plant workers. Note that, “Air that is saturated with moderator water at 35°C can give 3 000 mSv/h of tritium to an unprotected worker (See also: J.U.Burnham. Radiation Protection). The best protection from tritium can be achieved using an air-supplied respirator. Tritium cartridge respirators protects workers only by a factor of 3. The only way to reduce the skin absorption is by wearing plastics. In PHWR power plants, workers must wear plastics for work in atmospheres containing more than 500 μSv/h.
Consistency in all Risks
Finally, it is all about the risks arising from exposure to ionizing radiation and about the consistency in all risks of everyday life. In general, danger (also risk or peril) is the possibility of something bad happening. A situation in which there is a risk of something bad happening, is called dangerous, risky or perilous. Yes, the term ionizing radiation sounds very dangerous, but how exactly dangerous radiation is?
Humans are often inconsistent in our treatment of perceived risks. Even though two situations may have similar risks, people will find one situation permissible and another unjustifiably dangerous. For radiation risks, doses to the public must be kept under 1 mSv/year. Even for very conservative case of linear non-threshold assumption, one millisievert represents a 0.0055% chance of some detrimental health effects. Two points:
In our opinion, this is an acceptable risk. Note that, annual doses from natural background radiation in on average about 3.7 mSv/year (10 µSv = average daily dose received from natural background).
Moreover, problem of this model is that it neglects a number of defence biological processes that may be crucial at low doses. The research during the last two decades is very interesting and shows that small doses of radiation given at a low dose rate stimulate the defense mechanisms.
Annually received dose of 1 mSv causes very conservatively about 0.0055% chance of some detrimental health effects. In April 2012, a year after the Fukushima accident, cleanup efforts are supposed to be happening wherever the radiation dose exceeds government regulations. Entire towns are still off limits because the annual dose from the ground is projected to be greater than 50 mSv or even 20 mSv, leaving many people in the area homeless and jobless. But did anyone take into account health effects of this evacuation. The consequences of low-level radiation are often more psychological than radiological. Forced evacuation from a radiological or nuclear accident may lead to social isolation, anxiety, depression, psychosomatic medical problems, reckless behavior, even suicide. Such was the outcome of the 1986 Chernobyl nuclear disaster in Ukraine. A comprehensive 2005 study concluded that “the mental health impact of Chernobyl is the largest public health problem unleashed by the accident to date”. But what if the threshold model is true, and doses of up to 100 mSv/yr actually result in no detectable health risks? This would mean that people are being unnecessarily kept away and prevented from working on their farms for negligible health effects. Recall that the annual dose in some parts of Araxa, Brazil is higher than 20 mSv while the average dose examined in the three-country nuclear worker studies was 30-40 mSv/yr, and that these studies found no significant increase in solid cancers or leukemias from those doses.
Another point of view can be obtained when we will consider all risks of everyday life. What about risks, which arise from transportation. Nearly 1.25 million people die in road crashes each year, on average 3,287 deaths a day. Road crashes are the leading cause of death among young people ages 15-29, and the second leading cause of death worldwide among young people ages 5-14. On a road, people don’t realize the kinetic energy of a car. So why we do not stop driving cars? Yes, transportation is today essential, but so are the peaceful uses of radiation. And what about smoking cigarettes? Cigarettes contain also polonium-210, originating from the decay products of radon, which stick to tobacco leaves. Polonium-210 emits a 5.3 MeV alpha particle, which provides most of equivalent dose. Heavy smoking results in a dose of 160 mSv/year to localized spots at the bifurcations of segmental bronchi in the lungs from the decay of polonium-210. This dose is not readily comparable to the radiation protection limits, since the latter deal with whole body doses, while the dose from smoking is delivered to a very small portion of the body.
Finally, we would like to discuss a very interesting fact. It is generally known, the increasing use of nuclear power and electricity generation using nuclear reactors will lead to a small but increasing radiation dose to the general public. But it is not generally known, power generation from coal also creates additional exposures, and, what is more interesting, while exposure levels are very low, the coal cycle contributes more than half of the total radiation dose to the global population from electricity generation. The nuclear fuel cycle contributes less than one-fifth of this. The collective dose, which are defined as the sum of all individual effective doses in a group of people over the time period or during the operation being considered due to ionizing radiation, is:
670-1400 manSv for coal cycle, depending on the age of the power plant,
130 man Sv for nuclear fuel cycle,
5-160 man Sv for geothermal power,
55 man Sv for natural gas
03 man Sv for oil
Yes, these results should be seen from the perspective of the share of each technology in worldwide electricity production. Since 40 per cent of the world’s energy was produced by the coal cycle in 2010, and 13 per cent by nuclear, the normalized collective dose will be about the same:
7 – 1.4 man Sv/GW.a (man sievert per gigawatt year) for coal cycle
43 man Sv/GW.a (man sievert per gigawatt year) for nuclear fuel cycle
Special Reference: Sources and effects of ionizing radiation, UNSCEAR 2016 – Annex B. New York, 2017. ISBN: 978-92-1-142316-7.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation
We hope, this article, Danger of Ionizing Radiation – How Dangerous is Radiation, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
The weak force and the electromagnetic force are two the four fundamental forces. They are very different. This article summarizes these differences.
Weak Interaction – Weak Force
The weak interaction or weak force is one of the four fundamental forces and involves the exchange of the intermediate vector bosons, the W and the Z. Since these bosons are very massive (on the order of 80 GeV, the uncertainty principle dictates a range of about 10-18meters which is less than the diameter of a proton. As a result, the weak interaction takes place only at very small, sub-atomic distances.
The weak interaction responsible for some nuclear phenomena such as beta decay, which can be understood in terms of the weak force operating on the quarks within the neutron. One of two down quarks changes into an up quark by emitting a W– boson (carries away a negative charge). The W– boson then decays into a beta particle and an antineutrino. This process is equivalent to the process, in which a neutrino interacts with a neutron.
Electromagnetic Interaction – Electromagnetic Force
The electromagnetic force is the force responsible for all electromagnetic processes. It acts between electrically charged particles. It is infinite-ranged force, much stronger than gravitational force, obeys the inverse square law, but neither electricity nor magnetism adds up in the way that gravitational force does. Since there are positive and negative charges (poles), these charges tend to cancel each other out. Electromagnetism includes the electrostatic force acting between charged particles at rest, and the combined effect of electric and magnetic forces acting between charged particles moving relative to each other.
The photon, the quantum of electromagnetic radiation, is an elementary particle, which is the force carrier of the electromagnetic force. Photons are gauge bosons having no electric charge or rest mass and one unit of spin. Common to all photons is the speed of light, the universal constant of physics. In empty space, the photon moves at c (the speed of light – 299 792 458 metres per second).
Forces between static electrically charged particles are governed by the Coulomb’s law. Coulomb’s Law can be used to calculate the force between charged particles (e.g. two protons). The electrostatic force is directly proportional to the electrical charges of the two particles and inversely proportional to the square of the distance between the particles. Coulomb’s Law is stated as the following equation.
Both, the Coulomb’s law and the magnetic force, are summarized in the Lorentz force law. Fundamentally, both magnetic and electric forces are manifestations of an exchange force involving the exchange of photons.
The electromagnetic force plays a major role in determining the internal properties of most objects encountered in daily life. The chemical properties of atoms and molecules are determined by the number of protons, in fact, by number and arrangement of electrons.
Weak Force vs Electromagnetic Force
References:
Nuclear and Reactor Physics:
J. R. Lamarsh, Introduction to Nuclear Reactor Theory, 2nd ed., Addison-Wesley, Reading, MA (1983).
J. R. Lamarsh, A. J. Baratta, Introduction to Nuclear Engineering, 3d ed., Prentice-Hall, 2001, ISBN: 0-201-82498-1.
W. M. Stacey, Nuclear Reactor Physics, John Wiley & Sons, 2001, ISBN: 0- 471-39127-1.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
Advanced Reactor Physics:
K. O. Ott, W. A. Bezella, Introductory Nuclear Reactor Statics, American Nuclear Society, Revised edition (1989), 1989, ISBN: 0-894-48033-2.
K. O. Ott, R. J. Neuhold, Introductory Nuclear Reactor Dynamics, American Nuclear Society, 1985, ISBN: 0-894-48029-4.
D. L. Hetrick, Dynamics of Nuclear Reactors, American Nuclear Society, 1993, ISBN: 0-894-48453-2.
E. E. Lewis, W. F. Miller, Computational Methods of Neutron Transport, American Nuclear Society, 1993, ISBN: 0-894-48452-4.
See also:
Weak Force
We hope, this article, Weak Force vs Electromagnetic Force, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
The electromagnetic force and the gravitational force are two the four fundamental forces. They are very different. This article summarizes these differences.
Electromagnetic Interaction – Electromagnetic Force
The electromagnetic force is the force responsible for all electromagnetic processes. It acts between electrically charged particles. It is infinite-ranged force, much stronger than gravitational force, obeys the inverse square law, but neither electricity nor magnetism adds up in the way that gravitational force does. Since there are positive and negative charges (poles), these charges tend to cancel each other out. Electromagnetism includes the electrostatic force acting between charged particles at rest, and the combined effect of electric and magnetic forces acting between charged particles moving relative to each other.
The photon, the quantum of electromagnetic radiation, is an elementary particle, which is the force carrier of the electromagnetic force. Photons are gauge bosons having no electric charge or rest mass and one unit of spin. Common to all photons is the speed of light, the universal constant of physics. In empty space, the photon moves at c (the speed of light – 299 792 458 metres per second).
Forces between static electrically charged particles are governed by the Coulomb’s law. Coulomb’s Law can be used to calculate the force between charged particles (e.g. two protons). The electrostatic force is directly proportional to the electrical charges of the two particles and inversely proportional to the square of the distance between the particles. Coulomb’s Law is stated as the following equation.
Both, the Coulomb’s law and the magnetic force, are summarized in the Lorentz force law. Fundamentally, both magnetic and electric forces are manifestations of an exchange force involving the exchange of photons.
The electromagnetic force plays a major role in determining the internal properties of most objects encountered in daily life. The chemical properties of atoms and molecules are determined by the number of protons, in fact, by number and arrangement of electrons.
Gravitational Interaction – Gravitational Force
Gravity was the first force to be investigated scientifically. The gravitational force was described systematically by Isaac Newton in the 17th century. Newton stated that the gravitational force acts between all objects having mass (including objects ranging from atoms and photons, to planets and stars) and is directly proportional to the masses of the bodies and inversely proportional to the square of the distance between the bodies. Since energy and mass are equivalent, all forms of energy (including light) cause gravitation and are under the influence of it. The range of this force is ∞ and it is weaker than the other forces. This relationship is shown in the equation below.
The equation illustrates that the larger the masses of the objects or the smaller the distance between the objects, the greater the gravitational force. So even though the masses of nucleons are very small, the fact that the distance between nucleons is extremely short may make the gravitational force significant. The gravitational force between two protons that are separated by a distance of 10-20 meters is about 10-24 newtons. Gravity is the weakest of the four fundamental forces of physics, approximately 1038 times weaker than the strong force. On the other hand, gravity is additive. Every speck of matter that you put into a lump contributes to the overall overall gravity of the lump. Since it is also a very long range force, it is dominant force at the macroscopic scale, and is the cause of the formation, shape and trajectory (orbit) of astronomical bodies.
Electromagnetic Force vs Gravitational Force
References:
Nuclear and Reactor Physics:
J. R. Lamarsh, Introduction to Nuclear Reactor Theory, 2nd ed., Addison-Wesley, Reading, MA (1983).
J. R. Lamarsh, A. J. Baratta, Introduction to Nuclear Engineering, 3d ed., Prentice-Hall, 2001, ISBN: 0-201-82498-1.
W. M. Stacey, Nuclear Reactor Physics, John Wiley & Sons, 2001, ISBN: 0- 471-39127-1.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
Advanced Reactor Physics:
K. O. Ott, W. A. Bezella, Introductory Nuclear Reactor Statics, American Nuclear Society, Revised edition (1989), 1989, ISBN: 0-894-48033-2.
K. O. Ott, R. J. Neuhold, Introductory Nuclear Reactor Dynamics, American Nuclear Society, 1985, ISBN: 0-894-48029-4.
D. L. Hetrick, Dynamics of Nuclear Reactors, American Nuclear Society, 1993, ISBN: 0-894-48453-2.
E. E. Lewis, W. F. Miller, Computational Methods of Neutron Transport, American Nuclear Society, 1993, ISBN: 0-894-48452-4.
See also:
Electromagnetic Force
We hope, this article, Electromagnetic Force vs Gravitational Force, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.