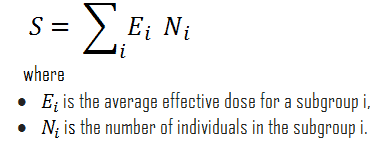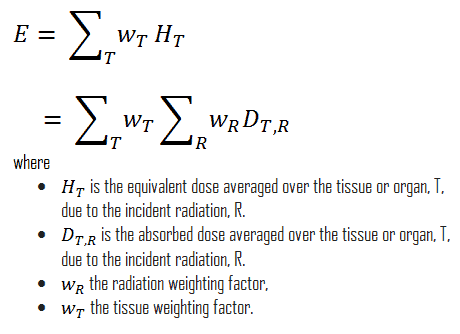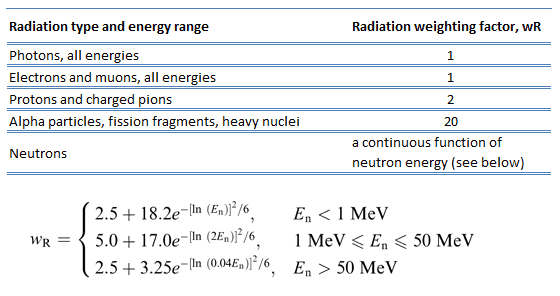As can be seen from the LNT dose-effect curve, the risk does not start at 0 because there is some risk of cancer, even with no occupational exposure. Radiation Dosimetry
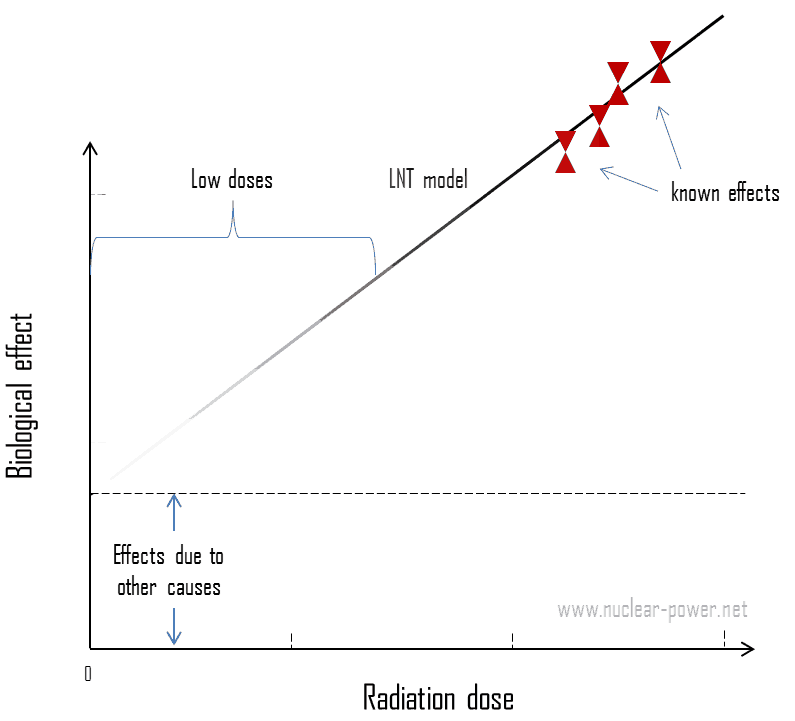
LNT model allows for the extrapolation of the cancer risk vs. radiation dose to low-dose levels, given a known risk at a high dose.
As can be seen from the LNT dose-effect curve, the risk does not start at 0 because there is some risk of cancer, even with no occupational exposure. Note that, radiation is one of physical carcinogenic agents, while cigarettes are an example of a chemical cancer causing agent. Viruses are examples of biological carcinogenic agents. The slope of the line just means that a person that receives 5 mSv in a year incurs 10 times as much risk as a person that receives 0.5 mSv in a year.
As can be seen the linear no-threshold model assumes that more exposure means more risk, and there is no dose of radiation so small that it will not have some effect.
The LNT model is recommended by the ICRP and accepted by most radiation protection authorities in the world. It must be emphasized, conservativeness of this model has enormous consequences and a number of organisations disagree with using the linear no-threshold model to estimate risk from environmental and occupational low-level radiation exposure. This principle was introduced in the late 1950s and is still the basis for all dose limits recommended.
According to ICRP:
“A dose-response model which is based on the assumption that, in the low dose range, radiation doses greater than zero will increase the risk of excess cancer and/or heritable disease in a simple proportionate manner.“
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Today the protection system is based on the LNT-hypothesis, assuming that all radiation is bad and that the deleterious effect (essentially the cancer risk) increases linearly with dose with no threshold (start at zero dose). Since zero dose is not attainable the ALARA – principle (As Low As Reasonable Achievable) was introduced. This allows the summation by dosimeters of all radiation exposure, without taking into consideration dose levels or dose rates. However, the aggregation of very low individual doses over extended time periods is inappropriate, and in particular, the calculation of the number of cancer deaths based on collective effective doses from trivial individual doses should be avoided.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
LNT
We hope, this article, LNT Model – Dose-effect Curve, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
The linear no-threshold model (LNT model) is a conservative model used in radiation protection to estimate the health effects from small radiation doses. Radiation Dosimetry
LNT model allows for the extrapolation of the cancer risk vs. radiation dose to low-dose levels, given a known risk at a high dose.
The linear no-threshold model (LNT model) is a conservative model used in radiation protection to estimate the health effects from small radiation doses. According to the LNT model, radiation is always considered harmful with no safety threshold, and the sum of several very small exposures are considered to have the same biological risk as one larger exposure (linearity). The problem is that, at very low doses, it is practically impossible to correlate any irradiation with certain biological effects. This is because the baseline cancer rate is already very high and the risk of developing cancer fluctuates 40% because of individual life style and environmental effects, obscuring the subtle effects of low-level radiation. Therefore it is very difficult to validate this model. Since data for low doses region are not available, biological effects for low doses of radiation must be therefore extrapolated. The question is how?
The LNT model is recommended by the ICRP and accepted by most radiation protection authorities in the world. It must be emphasized, conservativeness of this model has enormous consequences and a number of organisations disagree with using the linear no-threshold model to estimate risk from environmental and occupational low-level radiation exposure. This principle was introduced in the late 1950s and is still the basis for all dose limits recommended.
According to ICRP:
“A dose-response model which is based on the assumption that, in the low dose range, radiation doses greater than zero will increase the risk of excess cancer and/or heritable disease in a simple proportionate manner.“
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Today the protection system is based on the LNT-hypothesis, assuming that all radiation is bad and that the deleterious effect (essentially the cancer risk) increases linearly with dose with no threshold (start at zero dose). Since zero dose is not attainable the ALARA – principle (As Low As Reasonable Achievable) was introduced. This allows the summation by dosimeters of all radiation exposure, without taking into consideration dose levels or dose rates. However, the aggregation of very low individual doses over extended time periods is inappropriate, and in particular, the calculation of the number of cancer deaths based on collective effective doses from trivial individual doses should be avoided.
LNT model allows for the extrapolation of the cancer risk vs. radiation dose to low-dose levels, given a known risk at a high dose.
As can be seen from the LNT dose-effect curve, the risk does not start at 0 because there is some risk of cancer, even with no occupational exposure. Note that, radiation is one of physical carcinogenic agents, while cigarettes are an example of a chemical cancer causing agent. Viruses are examples of biological carcinogenic agents. The slope of the line just means that a person that receives 5 mSv in a year incurs 10 times as much risk as a person that receives 0.5 mSv in a year.
As can be seen the linear no-threshold model assumes that more exposure means more risk, and there is no dose of radiation so small that it will not have some effect.
Consequences of LNT model
Today the protection system is based on the LNT-hypothesis, assuming that all radiation is bad and that the deleterious effect (essentially the cancer risk) increases linearly with dose with no threshold (start at zero dose). The probabilistic nature of stochastic effects and the properties of the LNT model make it impossible to derive a clear distinction between ‘safe’ and ‘dangerous’, and this creates some difficulties in explaining the control of radiation risks. The major consequence of the LNT model is that some finite risk, however small, must be assumed and a level of protection established based on what is deemed acceptable. Since zero dose is not attainable, the ICRP (Publication 103) defines the System of Radiological Protection, which is based on the following three principles:
Justification. “Any decision that alters the radiation exposure situation should do more good than harm.”
Optimisation of Protection. “Doses should all be kept as low as reasonably achievable, taking into account economic and societal factors.” (known as ALARA or ALARP)
Dose Limitation. “The total dose to any individual … should not exceed the appropriate limits.”
All of these three principles have bases in the LNT model and the Commission considers that the LNT model remains a prudent basis for radiological protection at low doses and low dose rates.
LNT and Collective Dose
In case of collective dose, conservativeness of the LNT model has enormous consequences and the model is sometimes wrongly (perhaps intentionally) used to quantify the cancerous effect of collective doses of low-level radioactive contamination. A linear dose-effect curve makes it possible to use collective doses to calculate the detrimental effects to an irradiated population. Simply:
But what does it mean? If ten million people receives an effective dose of 0.1 µSv (an equivalent of eating one banana), then the collective dose will be S = 1 Sv. Does it mean there is 5.5% chance of developing cancer for one person due to eating bananas? Note that, for high doses one sievert represents a 5.5% chance of developing cancer. A number of organisations disagree with this result and with using the linear no-threshold model to estimate risk from environmental and occupational low-level radiation exposure. There is a question, whether the collective dose is meaningful at all.
The ICRP alone states:
“The collective effective dose quantity is an instrument for optimisation, for comparing radiological technologies and protection procedures, predominantly in the context of occupational exposure. Collective effective dose is not intended as a tool for epidemiological risk assessment, and it is inappropriate to use it in risk projections. The aggregation of very low individual doses over extended time periods is inappropriate, and in particular, the calculation of the number of cancer deaths based on collective effective doses from trivial individual doses should be avoided.”
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Controversy of LNT Model
As was written, today the protection system is based on the LNT-hypothesis, which is a conservative model used in radiation protection to estimate the health effects from small radiation doses. This model is excellent for setting up a protection system for all use of ionizing radiation. This model assumes, that there is no threshold point and risk increases linearly with a dose, i.e. the LNT model implies that there is no safe dose of ionizing radiation. If this linear model is correct, then natural background radiation is the most hazardous source of radiation to general public health, followed by medical imaging as a close second.
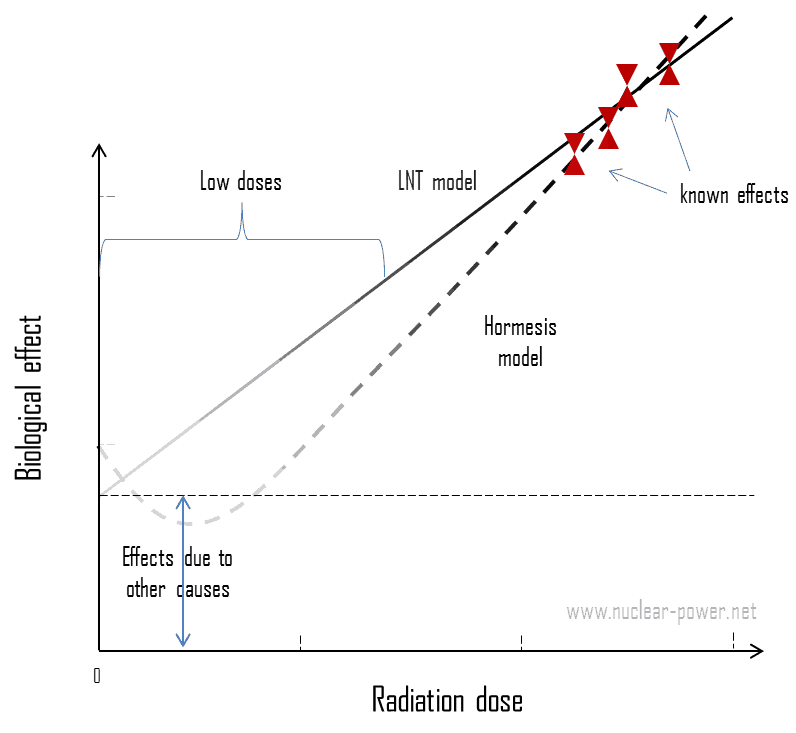
Alternative assumptions for the extrapolation of the cancer risk vs. radiation dose to low-dose levels, given a known risk at a high dose: LNT model, and hormesis model.
In case of low doses, its conservativeness has enormous consequences and the model is sometimes wrongly (perhaps intentionally) used to quantify the cancerous effect of collective doses of low-level radioactive contaminations. A linear dose-effect curve makes it possible to use collective doses to calculate the detrimental effects to an irradiated population. It is also argued that LNT model had caused an irrational fear of radiation, since every microsievert can be converted to the probability of cancer induction, however small this probability is. For example, if ten million people receives an effective dose of 0.1 µSv (an equivalent of eating one banana), then the collective dose will be S = 1 Sv. Does it mean there is 5.5% chance of developing cancer for one person due to eating banana? Note that, for high doses one sievert represents a 5.5% chance of developing cancer.
Problem of this model is that it neglects a number of defence biological processes that may be crucial at low doses. The research during the last two decades is very interesting and show that small doses of radiation given at a low dose rate stimulate the defense mechanisms. Therefore the LNT model is not universally accepted with some proposing an adaptive dose–response relationship where low doses are protective and high doses are detrimental. Many studies have contradicted the LNT model and many of these have shown adaptive response to low dose radiation resulting in reduced mutations and cancers. This phenomenon is known as radiation hormesis.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiobiology
We hope, this article, Linear no-threshold model, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
The biological effects of radiation on people can be grouped into somatic and hereditary effects. Somatic effects are those suffered by the exposed person. Hereditary effects are those suffered by the offspring of the individual exposed. Radiation Dosimetry
Stochastic effects of ionizing radiation occur by chance, generally occurring without a threshold level of dose. Probability of occurrence of stochastic effects is proportional to the dose but the severity of the effect is independent of the dose received. The biological effects of radiation on people can be grouped into somatic and hereditary effects. Somatic effects are those suffered by the exposed person. Hereditary effects are those suffered by the offspring of the individual exposed. Cancer risk is usually mentioned as the main stochastic effect of ionizing radiation, but also hereditary disorders are stochastic effects.
According to ICRP:
(83) On the basis of these calculations the Commission proposes nominal probability coefficients for detriment-adjusted cancer risk as 5.5 x 10⁻² Sv-1 for the whole population and 4.1 x 10⁻² Sv-1 for adult workers. For heritable effects, the detriment-adjusted nominal risk in the whole population is estimated as 0.2 x 10⁻² Sv-1 and in adult workers as 0.1 x 10⁻² Sv-1 .
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
The SI unit for effective dose, the sievert, represents the equivalent biological effect of the deposit of a joule of gamma rays energy in a kilogram of human tissue. As a result, one sievert represents a 5.5% chance of developing cancer. Note that, the effective dose is not intended as a measure of deterministic health effects, which is the severity of acute tissue damage that is certain to happen, that is measured by the quantity absorbed dose.
There are three general categories of stochastic effects resulting from exposure to low doses of radiation. These are:
Genetic effects. The genetic effect is suffered by the offspring of the individual exposed. It involves the mutation of very specific cells, namely the sperm or egg cells. Radiation is an example of a physical mutagenic agent. Note that, there are also many chemical agents as well as biological agents (such as viruses) that cause mutations. One very important fact to remember is that radiation increases the spontaneous mutation rate, but does not produce any new mutations.
Somatic effects. Somatic effects are those suffered by the exposed person. The most common impact of irradiation is the stochastic induction of cancer with a latent period of years or decades after exposure. Since cancer is the primary result, it is sometimes called the carcinogenic effect. Radiation is an example of a physical carcinogenic, while cigarettes are an example of a chemical cancer causing agent. Viruses are examples of biological carcinogenic agents.
In-Utero effects involve the production of malformations in developing embryos. However, this is actually a special case of the somatic effect, since the embryo/fetus is the one exposed to the radiation.
Somatic effects as a result of exposure to radiation are thought by most to occur in a stochastic manner. The most widely accepted model posits that the incidence of cancers due to ionizing radiation increases linearly with effective radiation dose at a rate of 5.5% per sievert. This model is known as the linear no-threshold model (LNT). This model assumes, that there is no threshold point and risk increases linearly with a dose. If this linear model is correct, then natural background radiation is the most hazardous source of radiation to general public health, followed by medical imaging as a close second. The LNT is not universally accepted with some proposing an adaptive dose–response relationship where low doses are protective and high doses are detrimental. It must be emphasized, that a number of organisations disagree with using the linear no-threshold model to estimate risk from environmental and occupational low-level radiation exposure.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiobiology
We hope, this article, Somatic Effect – Hereditary Effect – Ionizing Radiation, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
In radiation protection, dose limits are set to limit stochastic effects to an acceptable level, and to prevent deterministic effects completely. Stochastic Effects and Dose Limits
Stochastic effects of ionizing radiation occur by chance, generally occurring without a threshold level of dose. Probability of occurrence of stochastic effects is proportional to the dose but the severity of the effect is independent of the dose received. The biological effects of radiation on people can be grouped into somatic and hereditary effects. Somatic effects are those suffered by the exposed person. Hereditary effects are those suffered by the offspring of the individual exposed. Cancer risk is usually mentioned as the main stochastic effect of ionizing radiation, but also hereditary disorders are stochastic effects.
According to ICRP:
(83) On the basis of these calculations the Commission proposes nominal probability coefficients for detriment-adjusted cancer risk as 5.5 x 10⁻² Sv-1 for the whole population and 4.1 x 10⁻² Sv-1 for adult workers. For heritable effects, the detriment-adjusted nominal risk in the whole population is estimated as 0.2 x 10⁻² Sv-1 and in adult workers as 0.1 x 10⁻² Sv-1 .
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
The SI unit for effective dose, the sievert, represents the equivalent biological effect of the deposit of a joule of gamma rays energy in a kilogram of human tissue. As a result, one sievert represents a 5.5% chance of developing cancer. Note that, the effective dose is not intended as a measure of deterministic health effects, which is the severity of acute tissue damage that is certain to happen, that is measured by the quantity absorbed dose.
Stochastic Effects and Dose Limits
In radiation protection, dose limits are set to limit stochastic effects to an acceptable level, and to prevent deterministic effects completely. Note that, stochastic effects are those arising from chance: the greater the dose, the more likely the effect. Deterministic effects are those which normally have a threshold: above this, the severity of the effect increases with the dose. Dose limits are a fundamental component of radiation protection, and breaching these limits is against radiation regulation in most countries. Note that, the dose limits described in this article apply to routine operations. They do not apply to an emergency situation when human life is endangered. They do not apply in emergency exposure situations where an individual is attempting to prevent a catastrophic situation.
The limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
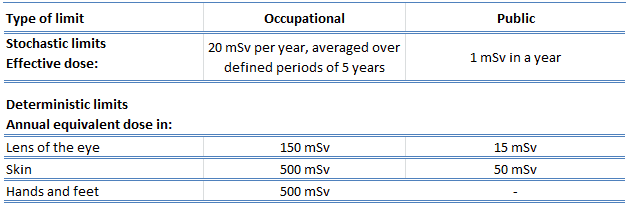
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Stochastic Effects
We hope, this article, Stochastic Effect and Dose Limit, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Stochastic Effects and Effective Dose. Effective dose allows to determine stochastic biological consequences of of all types of radiation. Radiation Dosimetry
Stochastic effects of ionizing radiation occur by chance, generally occurring without a threshold level of dose. Probability of occurrence of stochastic effects is proportional to the dose but the severity of the effect is independent of the dose received. The biological effects of radiation on people can be grouped into somatic and hereditary effects. Somatic effects are those suffered by the exposed person. Hereditary effects are those suffered by the offspring of the individual exposed. Cancer risk is usually mentioned as the main stochastic effect of ionizing radiation, but also hereditary disorders are stochastic effects.
Stochastic Effects and Effective Dose
The effective dose is defined as the doubly weighted sum of absorbed dose in all the organs and tissues of the body. It is very important, whether a person is exposed partially or completelly and it is very important, whether a person is exposed to gamma rays or to another type of radiation. Effective dose allows to determine stochastic biological consequences of of all types of radiation. Dose limits are set in terms of effective dose and apply to the individual for radiological protection purposes, including the assessment of risk in general terms. Mathematically, the effective dose can be expressed as:
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Stochastic Effects
We hope, this article, Stochastic Effect and Effective Dose, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
In radiation protection, dose limits are set to prevent deterministic effects completely and to limit stochastic effects to an acceptable level. Deterministic Effects and Dose Limits
Deterministic effects (or non-stochastic health effects) are health effects, that are related directly to the absorbed radiation dose and the severity of the effect increases as the dose increases. Deterministic effects have a threshold below which no detectable clinical effects do occur. The threshold may be very low (of the order of magnitude of 0.1 Gy or higher) and may vary from person to person. For doses between 0.25 Gy and 0.5 Gy slight blood changes may be detected by medical evaluations and for doses between 0.5 Gy and 1.5 Gy blood changes will be noted and symptoms of nausea, fatigue, vomiting occur.
Deterministic Effects and Dose Limits
In radiation protection, dose limits are set to limit stochastic effects to an acceptable level, and to prevent deterministic effects completely. Note that, stochastic effects are those arising from chance: the greater the dose, the more likely the effect. Deterministic effects are those which normally have a threshold: above this, the severity of the effect increases with the dose. Dose limits are a fundamental component of radiation protection, and breaching these limits is against radiation regulation in most countries. Note that, the dose limits described in this article apply to routine operations. They do not apply to an emergency situation when human life is endangered. They do not apply in emergency exposure situations where an individual is attempting to prevent a catastrophic situation.
The limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Deterministic Effects
We hope, this article, Deterministic Effect and Dose Limit, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
The lethal dose of radiation (LD) is an indication of the lethal amount radiation. In radiation protection, the median lethal dose, LDXY, is usually used. Radiation Dosimetry
The lethal dose of radiation (LD) is an indication of the lethal amount radiation. In radiation protection, the median lethal dose, LDXY, is usually used. For example, the dose of radiation expected to cause death to 50 % of the irradiated persons within 30 days is LD50/30. LD1 is the dose expected to cause death to 1% of the irradiated persons, consequently, LD99 is lethal for all (99%) persons irradiated. It is also very important, whether a person receives some medical treatment or not. The greater an acute radiation dose is, the greater is the possibility of it killing the individual. For a healthy adult, the LD50 is estimated to be somewhere between 3 and 5 Gy.
2.5 Sv – Dose that kills a human with a 1% risk (LD1), if the dose is received over a very short duration.
5 Sv – Dose that kills a human with a 50% risk within 30 days (LD50/30), if the dose is received over a very short duration. Cause of death will be loss of bone marrow function.
8 Sv – Dose that kills a human with a 99% risk (LD99), if the dose is received over a very short duration. At around 10 Gy, acute inflammation of the lungs can occur and lead to death.
The lethal dose data given above apply to acute gamma doses delivered in a very short time, e.g., a few minutes. More dose is required to produce the effects listed above, if the dose is received over a period of hours or longer.
Deterministic Effects and Dose Limits
In radiation protection, dose limits are set to limit stochastic effects to an acceptable level, and to prevent deterministic effects completely. Note that, stochastic effects are those arising from chance: the greater the dose, the more likely the effect. Deterministic effects are those which normally have a threshold: above this, the severity of the effect increases with the dose. Dose limits are a fundamental component of radiation protection, and breaching these limits is against radiation regulation in most countries. Note that, the dose limits described in this article apply to routine operations. They do not apply to an emergency situation when human life is endangered. They do not apply in emergency exposure situations where an individual is attempting to prevent a catastrophic situation.
The limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Deterministic Effects
We hope, this article, Lethal Dose of Radiation, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Radiation biology (also known as radiobiology) is a medical science that involves the study of biological effects of ionizing radiation on living tissues. Radiation Dosimetry
Radiation biology (also known as radiobiology) is a medical science that involves the study of biological effects of ionizing radiation on living tissues. Radiation is all around us. In, around, and above the world we live in. It is a natural energy force that surrounds us. It is a part of our natural world that has been here since the birth of our planet. Whether the source of radiation is natural or man-made, whether it is a large dose of radiation or a small dose, there will be some biological effects. In general, ionizing radiation is harmful and potentially lethal to living beings but can have health benefits in medicine, for example, in radiation therapy for the treatment of cancer and thyrotoxicosis. This chapter briefly summarizes the short and long term consequences which may result from exposure to radiation.
Cellular Damage – Radiobiology
All biological damage effects begin with the consequence of radiation interactions with the atoms forming the cells. All living things are composed of one or more cells. Every part of your body consists of cells or was built by them. Although we tend to think of biological effects in terms of the effect of radiation on living cells, in actuality, ionizing radiation, by definition, interacts only with atoms by a process called ionization. For ionizing radiation, the kinetic energy of particles (photons, electrons, etc.) of ionizing radiation is sufficient and the particle can ionize (to form ion by losing electrons) target atoms to form ions. Simply ionizing radiation can knock electrons from an atom.
There are two mechanisms by which radiation ultimately affects cells. These two mechanisms are commonly called:
Direct effects. Direct effects are caused by radiation, when radiation interacts directly with the atoms of the DNA molecule, or some other cellular component critical to the survival of the cell. The probability of the radiation interacting with the DNA molecule is very small since these critical components make up such a small part of the cell.
Indirect effects. Indirect effects are caused by interaction of radiation usually with water molecules. Each cell, just as is the case for the human body, is mostly water. Ionizing radiation may break the bonds that hold the water molecule together, producing radicals such as hydroxyl OH, superoxide anion O2–and others. These radicals can contribute to the destruction of the cell.
A large number of cells of any particular type is called a tissue. If this tissue forms a specialised functional unit, it is called an organ. The type and number of cells affected is also an important factor. Some cells and organs in the body are more sensitive to ionizing radiation than others.
Sensitivity of various types of cells to ionizing radiation is very high for tissues consisting of cells that divide rapidly like those found in bone marrow, stomach, intestines, male and female reproductive organs, and developing fetuses. This is because dividing cells require correct DNA information in order for the cell’s offspring to survive. A direct interaction of radiation with an active cell could result in the death or mutation of the cell, whereas a direct interaction with the DNA of a dormant cell would have less of an effect.
As a result, living cells can be classified according to their rate of reproduction, which also indicates their relative sensitivity to radiation. As a result, actively reproducing cells are more sensitive to ionizing radiation than cells that make up skin, kidney or liver tissue. The nerve and muscle cells are the slowest to regenerate and are the least sensitive cells.
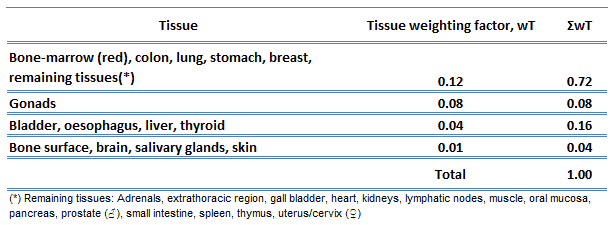
The sensitivity of the various organs of the human body correlate with the relative sensitivity of the cells from which they are composed. In practice, this sensitivity is represented by the tissue weighting factor, wT, which is the factor by which the equivalent dose in a tissue or organ T is weighted to represent the relative contribution of that tissue or organ to the total health detriment resulting from uniform irradiation of the body (ICRP 1991b).
If a person is irradiated only partially, the dose will depend strongly on the tissue, which was irradiated. For example, a 10 mSv gamma dose to the whole body and a 50 mSv dose to the thyroid is the same, in terms of risk, as a whole-body dose of 10 + 0.04 x 50 = 12 mSv.
High-LET and Low-LET Radiation
Source: ICRP Publ. 103: The 2007 Recommendations of the International Commission on Radiological Protection
As was written, each type of radiation interacts with matter in a different way. For example charged particles with high energies can directly ionize atoms. Alpha particles are fairly massive and carry a double positive charge, so they tend to travel only a short distance and do not penetrate very far into tissue if at all. However alpha particles will deposit their energy over a smaller volume (possibly only a few cells if they enter a body) and cause more damage to those few cells.
Beta particles (electrons) are much smaller than alpha particles. They carry a single negative charge. They are more penetrating than alpha particles. They can travel several meters but deposit less energy at any one point along their paths than alpha particles. This means beta particles tend to damage more cells, but with lesser damage to each. On the other hand electrically neutral particles interacts only indirectly, but can also transfer some or all of their energies to the matter.
It would certainly simplify matters if biological effects of radiation were directly proportional to the absorbed dose. Unfortunately, biological effects depend also on the way in which the absorbed dose is distributed along the path of the radiation. Studies have shown that alpha and neutron radiation cause greater biological damage for a given energy deposition per kg of tissue than gamma radiation does. It was discovered, biological effects of any radiation increases with the linear energy transfer (LET). In short, the biological damage from high-LET radiation (alpha particles, protons or neutrons) is much greater than that from low-LET radiation (gamma rays). This is because the living tissue can more easily repair damage from radiation that is spread over a large area than that which is concentrated in a small area. Of course, at very high levels of exposure gamma rays can still cause a great deal of damage to tissues.
Because more biological damage is caused for the same physical dose (i.e., the same energy deposited per unit mass of tissue), one gray of alpha or neutron radiation is more harmful than one gray of gamma radiation. This fact that radiations of different types (and energies) give different biological effects for the same absorbed dose is described in terms of factors known as the relative biological effectiveness (RBE) and the radiation weighting factor (wR).
Acute Dose and Chronic Dose
Biological effects of radiation and their consequences depends strongly on the level of dose rate obtained. In radiobiology, the dose rate is a measure of radiation dose intensity (or strength). Low-level doses are common for everyday life. In the following points there are a few examples of radiation exposure, which can be obtained from various sources.
05 µSv – Sleeping next to someone
09 µSv – Living within 30 miles of a nuclear power plant for a year
1 µSv – Eating one banana
3 µSv – Living within 50 miles of a coal power plant for a year
10 µSv – Average daily dose received from natural background
20 µSv – Chest X-ray
From biological consequences point of view, it is very important to distinguish between doses received over short and extended periods. Therefore, biological effects of radiation are typically divided into two categories.
Acute Doses. An “acute dose” (short-term high-level dose) is one that occurs over a short and finite period of time, i.e., within a day.
Chronic Doses. A “chronic dose” (long-term low-level dose) is a dose that continues for an extended period of time, i.e., weeks and months, so that it is better described by a dose rate.
High doses tend to kill cells, while low doses tend to damage or change them. High doses can cause visually dramatic radiation burns, and/or rapid fatality through acute radiation syndrome. Acute doses below 250 mGy are unlikely to have any observable effects. Acute doses of about 3 to 5 Gy have a 50% chance of killing a person some weeks after the exposure, if a person receives no medical treatment.
Low doses spread out over long periods of time don’t cause an immediate problem to any body organ. The effects of low doses of radiation occur at the level of the cell, and the results may not be observed for many years. Moreover, some studies demonstrate, most of human tissues exhibit a more pronounced tolerance to the effects of low-LET radiation in case of a prolonged exposure compared to a one-time exposure to a similar dose.
Deterministic and Stochastic Effects
In radiobiology, most adverse health effects of radiation exposure are usually divided into two broad classes:
Deterministic effects are threshold health effects, that are related directly to the absorbed radiation dose and the severity of the effect increases as the dose increases.
Stochastic effects occur by chance, generally occurring without a threshold level of dose. Probability of occurrence of stochastic effects is proportional to the dose but the severity of the effect is independent of the dose received.
Deterministic Effects
In radiobiology, deterministic effects (or non-stochastic health effects) are health effects, that are related directly to the absorbed radiation dose and the severity of the effect increases as the dose increases. Deterministic effects have a threshold below which no detectable clinical effects do occur. The threshold may be very low (of the order of magnitude of 0.1 Gy or higher) and may vary from person to person. For doses between 0.25 Gy and 0.5 Gy slight blood changes may be detected by medical evaluations and for doses between 0.5 Gy and 1.5 Gy blood changes will be noted and symptoms of nausea, fatigue, vomiting occur.
Once the threshold has been exceeded, the severity of an effect increases with dose. The reason for the presence of this threshold dose is that radiation damage (serious malfunction or death) of a critical population of cells (high doses tend to kill cells) in a given tissue needs to be sustained before injury is expressed in a clinically relevant form. Therefore, deterministic effects are also termed tissue reaction. They are also called non-stochastic effects to contrast with chance-like stochastic effects (e.g. cancer induction).
Deterministic effects are not necessarily more or less serious than stochastic effects. High doses can cause visually dramatic radiation burns, and/or rapid fatality through acute radiation syndrome. Acute doses below 250 mGy are unlikely to have any observable effects. Acute doses of about 3 to 5 Gy have a 50% chance of killing a person some weeks after the exposure, if a person receives no medical treatment. Deterministic effects can ultimately lead to a temporary nuisance or also to a fatality. Examples of deterministic effects:
Examples of deterministic effects are:
Acute radiation syndrome, by acute whole-body radiation
Radiation burns, from radiation to a particular body surface
Radiation-induced thyroiditis, a potential side effect from radiation treatment against hyperthyroidism
Chronic radiation syndrome, from long-term radiation.
Radiation-induced lung injury, from for example radiation therapy to the lungs
Lethal Doses of Radiation
The lethal dose of radiation (LD) is an indication of the lethal amount radiation. In radiation protection, the median lethal dose, LDXY is usually used. For example, the dose of radiation expected to cause death to 50 % of the irradiated persons within 30 days is LD50/30. LD1 is the dose expected to cause death to 1% of the irradiated persons, consequently, LD99 is lethal for all (99%) persons irradiated. It is also very important, whether a person receives some medical treatment or not. The greater an acute radiation dose is, the greater is the possibility of it killing the individual. For a healthy adult, the LD50 is estimated to be somewhere between 3 and 5 Gy.
2.5 Sv – Dose that kills a human with a 1% risk (LD1), if the dose is received over a very short duration.
5 Sv – Dose that kills a human with a 50% risk within 30 days (LD50/30), if the dose is received over a very short duration. Cause of death will be loss of bone marrow function.
8 Sv – Dose that kills a human with a 99% risk (LD99), if the dose is received over a very short duration. At around 10 Gy, acute inflammation of the lungs can occur and lead to death.
The lethal dose data given above apply to acute gamma doses delivered in a very short time, e.g., a few minutes. More dose is required to produce the effects listed above, if the dose is received over a period of hours or longer.
Stochastic Effects
In radiobiology, stochastic effects of ionizing radiation occur by chance, generally occurring without a threshold level of dose. Probability of occurrence of stochastic effects is proportional to the dose but the severity of the effect is independent of the dose received. The biological effects of radiation on people can be grouped into somatic and hereditary effects. Somatic effects are those suffered by the exposed person. Hereditary effects are those suffered by the offspring of the individual exposed. Cancer risk is usually mentioned as the main stochastic effect of ionizing radiation, but also hereditary disorders are stochastic effects.
According to ICRP:
(83) On the basis of these calculations the Commission proposes nominal probability coefficients for detriment-adjusted cancer risk as 5.5 x 10⁻² Sv-1 for the whole population and 4.1 x 10⁻² Sv-1 for adult workers. For heritable effects, the detriment-adjusted nominal risk in the whole population is estimated as 0.2 x 10⁻² Sv-1 and in adult workers as 0.1 x 10⁻² Sv-1 .
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
The SI unit for effective dose, the sievert, represents the equivalent biological effect of the deposit of a joule of gamma rays energy in a kilogram of human tissue. As a result, one sievert represents a 5.5% chance of developing cancer. Note that, the effective dose is not intended as a measure of deterministic health effects, which is the severity of acute tissue damage that is certain to happen, that is measured by the quantity absorbed dose.
There are three general categories of stochastic effects resulting from exposure to low doses of radiation. These are:
Genetic effects. The genetic effect is suffered by the offspring of the individual exposed. It involves the mutation of very specific cells, namely the sperm or egg cells. Radiation is an example of a physical mutagenic agent. Note that, there are also many chemical agents as well as biological agents (such as viruses) that cause mutations. One very important fact to remember is that radiation increases the spontaneous mutation rate, but does not produce any new mutations.
Somatic effects. Somatic effects are those suffered by the exposed person. The most common impact of irradiation is the stochastic induction of cancer with a latent period of years or decades after exposure. Since cancer is the primary result, it is sometimes called the carcinogenic effect. Radiation is an example of a physical carcinogenic, while cigarettes are an example of a chemical cancer causing agent. Viruses are examples of biological carcinogenic agents.
In-Utero effects involve the production of malformations in developing embryos. However, this is actually a special case of the somatic effect, since the embryo/fetus is the one exposed to the radiation.
Somatic effects as a result of exposure to radiation are thought by most to occur in a stochastic manner. The most widely accepted model posits that the incidence of cancers due to ionizing radiation increases linearly with effective radiation dose at a rate of 5.5% per sievert. This model is known as the linear no-threshold model (LNT). This model assumes, that there is no threshold point and risk increases linearly with a dose. If this linear model is correct, then natural background radiation is the most hazardous source of radiation to general public health, followed by medical imaging as a close second. The LNT is not universally accepted with some proposing an adaptive dose–response relationship where low doses are protective and high doses are detrimental. It must be emphasized, that a number of organisations disagree with using the linear no-threshold model to estimate risk from environmental and occupational low-level radiation exposure.
Radiobiology and Dose Limits
In radiation protection, dose limits are set to limit stochastic effects to an acceptable level, and to prevent deterministic effects completely. Note that, stochastic effects are those arising from chance: the greater the dose, the more likely the effect. Deterministic effects are those which normally have a threshold: above this, the severity of the effect increases with the dose. Dose limits are a fundamental component of radiation protection, and breaching these limits is against radiation regulation in most countries. Note that, the dose limits described in this article apply to routine operations. They do not apply to an emergency situation when human life is endangered. They do not apply in emergency exposure situations where an individual is attempting to prevent a catastrophic situation.
The limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Protection
We hope, this article, Radiobiology – Radiation Biology, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Deterministic and Stochastic Effects. Most adverse health effects of radiation exposure are usually divided into two broad classes: Deterministic and stochastic effects. Radiation Dosimetry
In radiation protection, most adverse health effects of radiation exposure are usually divided into two broad classes:
Deterministic effects are threshold health effects, that are related directly to the absorbed radiation dose and the severity of the effect increases as the dose increases.
Stochastic effects occur by chance, generally occurring without a threshold level of dose. Probability of occurrence of stochastic effects is proportional to the dose but the severity of the effect is independent of the dose received.
Deterministic Effects
Deterministic effects (or non-stochastic health effects) are health effects, that are related directly to the absorbed radiation dose and the severity of the effect increases as the dose increases. Deterministic effects have a threshold below which no detectable clinical effects do occur. The threshold may be very low (of the order of magnitude of 0.1 Gy or higher) and may vary from person to person. For doses between 0.25 Gy and 0.5 Gy slight blood changes may be detected by medical evaluations and for doses between 0.5 Gy and 1.5 Gy blood changes will be noted and symptoms of nausea, fatigue, vomiting occur.
Once the threshold has been exceeded, the severity of an effect increases with dose. The reason for the presence of this threshold dose is that radiation damage (serious malfunction or death) of a critical population of cells (high doses tend to kill cells) in a given tissue needs to be sustained before injury is expressed in a clinically relevant form. Therefore, deterministic effects are also termed tissue reaction. They are also called non-stochastic effects to contrast with chance-like stochastic effects (e.g. cancer induction).
Deterministic effects are not necessarily more or less serious than stochastic effects. High doses can cause visually dramatic radiation burns, and/or rapid fatality through acute radiation syndrome. Acute doses below 250 mGy are unlikely to have any observable effects. Acute doses of about 3 to 5 Gy have a 50% chance of killing a person some weeks after the exposure, if a person receives no medical treatment. Deterministic effects can ultimately lead to a temporary nuisance or also to a fatality. Examples of deterministic effects:
Examples of deterministic effects are:
Acute radiation syndrome, by acute whole-body radiation
Radiation burns, from radiation to a particular body surface
Radiation-induced thyroiditis, a potential side effect from radiation treatment against hyperthyroidism
Chronic radiation syndrome, from long-term radiation.
Radiation-induced lung injury, from for example radiation therapy to the lungs
Stochastic Effects
Stochastic effects of ionizing radiation occur by chance, generally occurring without a threshold level of dose. Probability of occurrence of stochastic effects is proportional to the dose but the severity of the effect is independent of the dose received. The biological effects of radiation on people can be grouped into somatic and hereditary effects. Somatic effects are those suffered by the exposed person. Hereditary effects are those suffered by the offspring of the individual exposed. Cancer risk is usually mentioned as the main stochastic effect of ionizing radiation, but also hereditary disorders are stochastic effects.
According to ICRP:
(83) On the basis of these calculations the Commission proposes nominal probability coefficients for detriment-adjusted cancer risk as 5.5 x 10⁻² Sv-1 for the whole population and 4.1 x 10⁻² Sv-1 for adult workers. For heritable effects, the detriment-adjusted nominal risk in the whole population is estimated as 0.2 x 10⁻² Sv-1 and in adult workers as 0.1 x 10⁻² Sv-1 .
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
The SI unit for effective dose, the sievert, represents the equivalent biological effect of the deposit of a joule of gamma rays energy in a kilogram of human tissue. As a result, one sievert represents a 5.5% chance of developing cancer. Note that, the effective dose is not intended as a measure of deterministic health effects, which is the severity of acute tissue damage that is certain to happen, that is measured by the quantity absorbed dose.
Biological Effects and Dose Limits
In radiation protection, dose limits are set to limit stochastic effects to an acceptable level, and to prevent deterministic effects completely. Note that, stochastic effects are those arising from chance: the greater the dose, the more likely the effect. Deterministic effects are those which normally have a threshold: above this, the severity of the effect increases with the dose. Dose limits are a fundamental component of radiation protection, and breaching these limits is against radiation regulation in most countries. Note that, the dose limits described in this article apply to routine operations. They do not apply to an emergency situation when human life is endangered. They do not apply in emergency exposure situations where an individual is attempting to prevent a catastrophic situation.
The limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiobiology
We hope, this article, Deterministic and Stochastic Effect, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Ionizing radiation safety is the science and practice of protecting people and the environment from the harmful effects of ionizing radiation. Radiation Dosimetry
ionizing radiation – hazard symbol
Ionizing radiation safety, i.e. radiation protection, is the science and practice of protecting people and the environment from the harmful effects of ionizing radiation. The International Atomic Energy Agency (IAEA) defines radiation protection as:
“The protection of people from harmful effects of exposure to ionizing radiation, and the means for achieving this”
It is a serious topic not only in nuclear power plants, but also in industry or in medical centres. According to the IAEA, radiation protection can be divided into three groups:
occupational radiation protection, which is the protection of workers in situations where their exposure is directly related to or required by their work
medical radiation protection, which is the protection of patients exposed to radiation as part of their diagnosis or treatment
public radiation protection, which is the protection of individual members of the public and of the population in general
According to the ICRP (Publication 103), the System of Radiological Protection is based on the following three principles:
Justification. “Any decision that alters the radiation exposure situation should do more good than harm.”
Optimisation of Protection. “Doses should all be kept as low as reasonably achievable, taking into account economic and societal factors.” (known as ALARA or ALARP)
Dose Limitation. “The total dose to any individual … should not exceed the appropriate limits.”
See also: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Ionizing radiation is any radiation (particles or electromagnetic waves) that carries enough energy to knock electrons from atoms or molecules, thereby ionizing them. For ionizing radiation, the kinetic energy of particles (photons, electrons, etc.) is sufficient and the particle can ionize (to form ion by losing electrons) target atoms to form ions.
The boundary between ionizing and non-ionizing radiation is not sharply defined, since different molecules and atoms ionize at different energies. This is typical for electromagnetic waves. Among electromagnetic waves belong, in order of increasing frequency (energy) and decreasing wavelength: radio waves, microwaves, infrared radiation, visible light, ultraviolet radiation, X-rays and gamma rays. Gamma rays, X-rays, and the higher ultraviolet part of the spectrum are ionizing, whereas the lower ultraviolet, visible light (including laser light), infrared, microwaves, and radio waves are considered non-ionizing radiation.
All biological damage effects begin with the consequence of radiation interactions with the atoms forming the cells. All living things are composed of one or more cells. Every part of your body consists of cells or was built by them. Although we tend to think of biological effects in terms of the effect of radiation on living cells, in actuality, ionizing radiation, by definition, interacts only with atoms by a process called ionization.
The danger of ionizing radiation lies in the fact that the radiation is invisible and not directly detectable by human senses. People can neither see nor feel radiation, yet it deposits energy to the molecules of the body. The energy is transferred in small quantities for each interaction between the radiation and a molecule and there are usually many such interactions.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation
We hope, this article, Ionizing Radiation Safety, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.