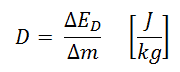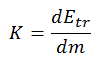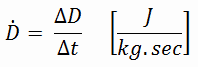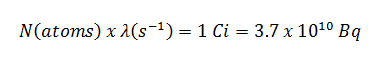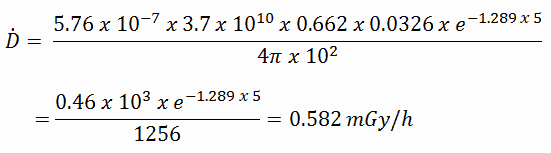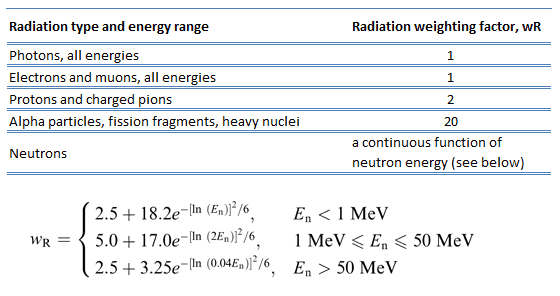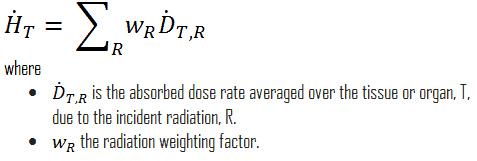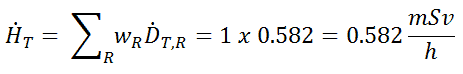In general, the ICRP defines operational quantities for area monitoring. The operational quantities for area monitoring are the ambient dose equivalent and the directional dose equivalent. Radiation Dosimetry
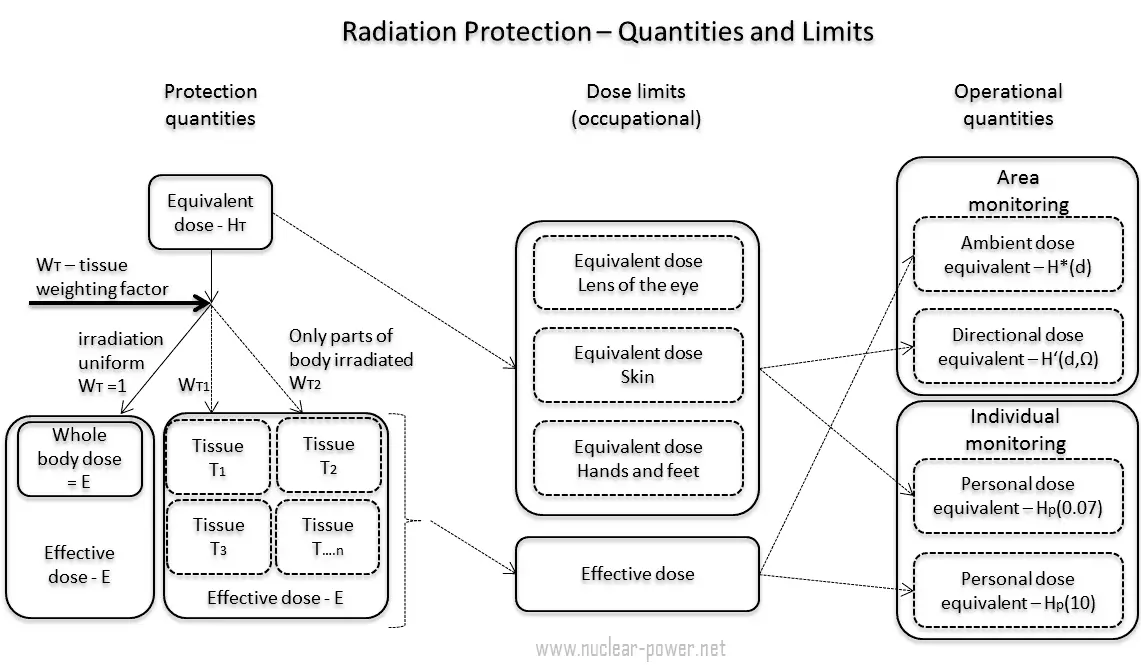
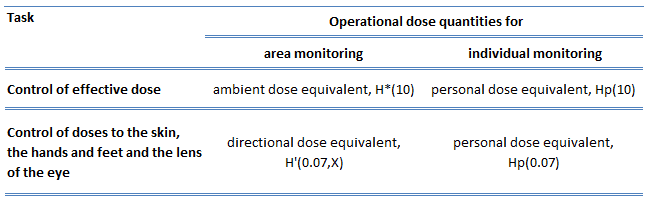
In general, the ICRP defines operational quantities for area and individual monitoring of external exposures. The operational quantities for area monitoring are:
Ambient dose equivalent, H*(10). The ambient dose equivalent is an operational quantity for area monitoring of strongly penetrating radiation.
Directional dose equivalent, H’ (d,Ω). The directional dose equivalent is an operational quantity for area monitoring of weakly penetrating radiation.
The operational quantities for individual monitoring are:
Personal dose equivalent, Hp(0.07). The Hp(0.07) dose equivalent is an operational quantity for individual monitoring for the assessment of the dose to the skin and to the hands and feet.
Personal dose equivalent, Hp(10). The Hp(10) dose equivalent is an operational quantity for individual monitoring for the assessment of effective dose.
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Area Monitoring
Ambient Dose Equivalent – H*(10)
The ambient dose equivalent is an operational quantity for area monitoring. According to the ICRP, the ambient dose equivalent is defined as:
ICRP Publication 103:
“The dose equivalent at a point in a radiation field that would be produced by the corresponding expanded and aligned field in the ICRU sphere at a depth of 10 mm on the radius vector opposing the direction of the aligned field.”
The ambient dose equivalent is given the symbol H*(10). The SI unit of H*(10) is the sievert(Sv). Unit of sievert was named after the Swedish scientist Rolf Sievert, who did a lot of the early work on dosimetry in radiation therapy. For all types of external radiation, the operational quantities for area monitoring are defined on the basis of a dose equivalent value at a point in a simple phantom, the ICRU sphere, which is a sphere of tissue-equivalent material (30 cm in diameter, ICRU (soft) tissue with density: 1 g/cm3 , and mass composition: 76.2% oxygen, 11.1% carbon, 10.1% hydrogen, and 2.6% nitrogen).
As was written, operational quantities are measurable unlike an effective dose, and instruments for radiation monitoring are calibrated in terms of these quantities. In monitoring, the values of these operational quantities are taken as a sufficiently precise assessment of effective dose and skin dose, respectively, in particular, if their values are below the protection limits. Numerical links between operational quantities and effective dose is represented by conservative conversion coefficients, which are defined for a reference person.
Directional Dose Equivalent – H’(d,Ω)
The directional dose equivalent is an operational quantity for area monitoring of weakly penetrating radiation. The directional dose equivalent, H’(d,Ω), is the operational quantity for determination of equivalent dose to skin, lens of the eye, etc., also for beta radiation and low-energy photons.
According to the ICRP, the directional dose equivalent is defined as:
ICRP Publication 103:
“The dose equivalent at a point in a radiation field that would be produced by the corresponding expanded field in the ICRU sphere at a depth, d, on a radius in a specified direction, Ω. ”
The directional dose equivalent is given the symbol H’ (0.07,Ω) or, in rare cases, H'(3,Ω). The SI unit of H’ (d,Ω) is the sievert(Sv). Unit of sievert was named after the Swedish scientist Rolf Sievert, who did a lot of the early work on dosimetry in radiation therapy. For all types of external radiation, the operational quantities for area monitoring are defined on the basis of a dose equivalent value at a point in a simple phantom, the ICRU sphere, which is a sphere of tissue-equivalent material (30 cm in diameter, ICRU (soft) tissue with density: 1 g/cm3 , and mass composition: 76.2% oxygen, 11.1% carbon, 10.1% hydrogen, and 2.6% nitrogen).
As was written, operational quantities are measurable unlike an effective dose, and instruments for radiation monitoring are calibrated in terms of these quantities. In monitoring, the values of these operational quantities are taken as a sufficiently precise assessment of effective dose and skin dose, respectively, in particular, if their values are below the protection limits. Numerical links between operational quantities and effective dose is represented by conservative conversion coefficients, which are defined for a reference person.
Dose limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
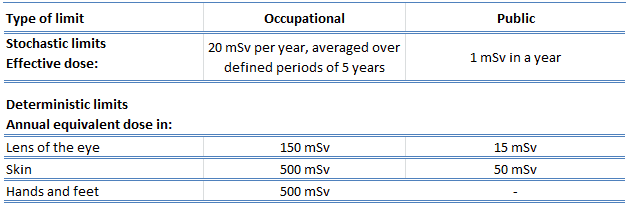
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Occupational Exposure – Effective Dose
In most situations of occupational exposure the effective dose, E, can be derived from operational quantities using the following formula:
The committed dose is a dose quantity that measures the stochastic health risk due to an intake of radioactive material into the human body.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Monitoring
We hope, this article, Area Monitoring – Radiation Protection, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
The ambient dose equivalent is an operational quantity for area monitoring. The ambient dose equivalent is given the symbol H*(10). The SI unit of H*(10) is the sievert (Sv). Radiation Dosimetry
Ambient Dose Equivalent – H*(10)
The ambient dose equivalent is an operational quantity for area monitoring. According to the ICRP, the ambient dose equivalent is defined as:
ICRP Publication 103:
“The dose equivalent at a point in a radiation field that would be produced by the corresponding expanded and aligned field in the ICRU sphere at a depth of 10 mm on the radius vector opposing the direction of the aligned field.”
The ambient dose equivalent is given the symbol H*(10). The SI unit of H*(10) is the sievert(Sv). Unit of sievert was named after the Swedish scientist Rolf Sievert, who did a lot of the early work on dosimetry in radiation therapy. For all types of external radiation, the operational quantities for area monitoring are defined on the basis of a dose equivalent value at a point in a simple phantom, the ICRU sphere, which is a sphere of tissue-equivalent material (30 cm in diameter, ICRU (soft) tissue with density: 1 g/cm3 , and mass composition: 76.2% oxygen, 11.1% carbon, 10.1% hydrogen, and 2.6% nitrogen).
As was written, operational quantities are measurable unlike an effective dose, and instruments for radiation monitoring are calibrated in terms of these quantities. In monitoring, the values of these operational quantities are taken as a sufficiently precise assessment of effective dose and skin dose, respectively, in particular, if their values are below the protection limits. Numerical links between operational quantities and effective dose is represented by conservative conversion coefficients, which are defined for a reference person.
Dose limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Occupational Exposure – Effective Dose
In most situations of occupational exposure the effective dose, E, can be derived from operational quantities using the following formula:
The committed dose is a dose quantity that measures the stochastic health risk due to an intake of radioactive material into the human body.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Monitoring
We hope, this article, Ambient Dose Equivalent – H*(10), helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
The directional dose equivalent is an operational quantity for area monitoring of weakly penetrating radiation. The directional dose equivalent, H’(d,Ω), is the operational quantity for determination of equivalent dose to skin, lens of the eye, etc. Radiation Dosimetry
Directional Dose Equivalent – H’(d,Ω)
The directional dose equivalent is an operational quantity for area monitoring of weakly penetrating radiation. The directional dose equivalent, H’(d,Ω), is the operational quantity for determination of equivalent dose to skin, lens of the eye, etc., also for beta radiation and low-energy photons.
According to the ICRP, the directional dose equivalent is defined as:
ICRP Publication 103:
“The dose equivalent at a point in a radiation field that would be produced by the corresponding expanded field in the ICRU sphere at a depth, d, on a radius in a specified direction, Ω. ”
The directional dose equivalent is given the symbol H’ (0.07,Ω) or, in rare cases, H'(3,Ω). The SI unit of H’ (d,Ω) is the sievert(Sv). Unit of sievert was named after the Swedish scientist Rolf Sievert, who did a lot of the early work on dosimetry in radiation therapy. For all types of external radiation, the operational quantities for area monitoring are defined on the basis of a dose equivalent value at a point in a simple phantom, the ICRU sphere, which is a sphere of tissue-equivalent material (30 cm in diameter, ICRU (soft) tissue with density: 1 g/cm3 , and mass composition: 76.2% oxygen, 11.1% carbon, 10.1% hydrogen, and 2.6% nitrogen).
As was written, operational quantities are measurable unlike an effective dose, and instruments for radiation monitoring are calibrated in terms of these quantities. In monitoring, the values of these operational quantities are taken as a sufficiently precise assessment of effective dose and skin dose, respectively, in particular, if their values are below the protection limits. Numerical links between operational quantities and effective dose is represented by conservative conversion coefficients, which are defined for a reference person.
Dose limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Occupational Exposure – Effective Dose
In most situations of occupational exposure the effective dose, E, can be derived from operational quantities using the following formula:
The committed dose is a dose quantity that measures the stochastic health risk due to an intake of radioactive material into the human body.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Monitoring
We hope, this article, Directional Dose Equivalent – H’(d,Ω), helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
In general, the ICRP defines operational quantities for area and individual monitoring. The operational quantities for individual monitoring are the personal dose equivalent, Hp(0.07) and Hp(10). Radiation Dosimetry
In general, the ICRP defines operational quantities for area and individual monitoring of external exposures. The operational quantities for area monitoring are:
Ambient dose equivalent, H*(10). The ambient dose equivalent is an operational quantity for area monitoring of strongly penetrating radiation.
Directional dose equivalent, H’ (d,Ω). The directional dose equivalent is an operational quantity for area monitoring of weakly penetrating radiation.
The operational quantities for individual monitoring are:
Personal dose equivalent, Hp(0.07). The Hp(0.07) dose equivalent is an operational quantity for individual monitoring for the assessment of the dose to the skin and to the hands and feet.
Personal dose equivalent, Hp(10). The Hp(10) dose equivalent is an operational quantity for individual monitoring for the assessment of effective dose.
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Individual Monitoring
Personal Dose Equivalent – Hp(10) – Hp(0.07)
Generally, the personal dose equivalent, Hp(d), is an operational quantity for individual monitoring. According to the ICRP, the personal dose equivalent is defined as:
ICRP Publication 103:
“The dose equivalent in soft tissue (commonly interpreted as the ‘ICRU sphere’) at an appropriate depth, d, below a specified point on the human body. ”
The personal dose equivalent is given the symbol Hp(d). Two common operational quantities for individual monitoring defined by the ICRP are:
Personal dose equivalent, Hp(0.07). The Hp(0.07) dose equivalent is an operational quantity for individual monitoring for the assessment of the dose to the skin and to the hands and feet.
Personal dose equivalent, Hp(10). The Hp(10) dose equivalent is an operational quantity for individual monitoring for the assessment of effective dose.
As can be seen, various depths can be used. The personal dose equivalent, Hp(d), can be assessed indirectly with a thin, tissue equivalent detector (radiation dosimeter) that is worn at the surface of the body and covered with an appropriate thickness of tissue equivalent material. The specified point, d, is normally taken to be where the radiation dosimeter is worn.
For assessment of superficial organs and the control of equivalent dose, depths of 0.07 mm for skin and 3 mm for the lens of the eye are employed, and the personal dose equivalents for those depths are denoted by Hp(0.07) and Hp(3), respectively. Hp(0.07) is also called the shallow dose equivalent.
For the assessment of deep organs and the control of effective dose, Hp(10) with a depth d = 10 mm is chosen. Hp(10) is also called the deep dose equivalent. If the personal dosimeter is worn on a position of the body representative of its exposure, at low doses and under the assumption of a uniform whole-body exposure, the value of Hp(10) provides an effective dose value sufficiently precise for radiological protection purposes. Neutron and gamma radiations contribute to both deep and shallow dose, but beta radiation is completely absorbed in the skin and therefore contributes to shallow dose only.
The SI unit of Hp(d) is the sievert (Sv). Unit of sievert was named after the Swedish scientist Rolf Sievert, who did a lot of the early work on dosimetry in radiation therapy. For all types of external radiation, the operational quantities for individual monitoring are defined on the basis of a dose equivalent value at a point in a simple phantom, the ICRU sphere, which is a sphere of tissue-equivalent material (30 cm in diameter, ICRU (soft) tissue with density: 1 g/cm3 , and mass composition: 76.2% oxygen, 11.1% carbon, 10.1% hydrogen, and 2.6% nitrogen).
As was written, operational quantities are measurable unlike an effective dose, and instruments for radiation monitoring are calibrated in terms of these quantities. In monitoring, the values of these operational quantities are taken as a sufficiently precise assessment of effective dose and skin dose, respectively, in particular, if their values are below the protection limits. Numerical links between operational quantities and effective dose is represented by conservative conversion coefficients, which are defined for a reference person. In most practical situations, dosimeters provide reasonable approximations to the personal dose equivalent, Hp(d), at least at the location of the dosimeter. It must be noted, the personal dose equivalent generally overestimates the effective dose. On the other hand, this procedure is valid only at low doses and under the assumption of a uniform whole-body exposure. For high personal doses approaching or exceeding the annual dose limit, or in strongly inhomogeneous radiation fields, however, this procedure might not be sufficient.
Dose limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Occupational Exposure – Effective Dose
In most situations of occupational exposure the effective dose, E, can be derived from operational quantities using the following formula:
The committed dose is a dose quantity that measures the stochastic health risk due to an intake of radioactive material into the human body.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Monitoring
We hope, this article, Individual Monitoring – Radiation Protection, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
The personal dose equivalent is given the symbol Hp(d). Two common operational quantities for individual monitoring defined by the ICRP are: Personal dose equivalent, Hp(0.07) and Hp(10). Radiation Dosimetry
Personal Dose Equivalent – Hp(10) – Hp(0.07)
Generally, the personal dose equivalent, Hp(d), is an operational quantity for individual monitoring. According to the ICRP, the personal dose equivalent is defined as:
ICRP Publication 103:
“The dose equivalent in soft tissue (commonly interpreted as the ‘ICRU sphere’) at an appropriate depth, d, below a specified point on the human body. ”
The personal dose equivalent is given the symbol Hp(d). Two common operational quantities for individual monitoring defined by the ICRP are:
Personal dose equivalent, Hp(0.07). The Hp(0.07) dose equivalent is an operational quantity for individual monitoring for the assessment of the dose to the skin and to the hands and feet.
Personal dose equivalent, Hp(10). The Hp(10) dose equivalent is an operational quantity for individual monitoring for the assessment of effective dose.
As can be seen, various depths can be used. The personal dose equivalent, Hp(d), can be assessed indirectly with a thin, tissue equivalent detector (radiation dosimeter) that is worn at the surface of the body and covered with an appropriate thickness of tissue equivalent material. The specified point, d, is normally taken to be where the radiation dosimeter is worn.
For assessment of superficial organs and the control of equivalent dose, depths of 0.07 mm for skin and 3 mm for the lens of the eye are employed, and the personal dose equivalents for those depths are denoted by Hp(0.07) and Hp(3), respectively. Hp(0.07) is also called the shallow dose equivalent.
For the assessment of deep organs and the control of effective dose, Hp(10) with a depth d = 10 mm is chosen. Hp(10) is also called the deep dose equivalent. If the personal dosimeter is worn on a position of the body representative of its exposure, at low doses and under the assumption of a uniform whole-body exposure, the value of Hp(10) provides an effective dose value sufficiently precise for radiological protection purposes. Neutron and gamma radiations contribute to both deep and shallow dose, but beta radiation is completely absorbed in the skin and therefore contributes to shallow dose only.
The SI unit of Hp(d) is the sievert (Sv). Unit of sievert was named after the Swedish scientist Rolf Sievert, who did a lot of the early work on dosimetry in radiation therapy. For all types of external radiation, the operational quantities for individual monitoring are defined on the basis of a dose equivalent value at a point in a simple phantom, the ICRU sphere, which is a sphere of tissue-equivalent material (30 cm in diameter, ICRU (soft) tissue with density: 1 g/cm3 , and mass composition: 76.2% oxygen, 11.1% carbon, 10.1% hydrogen, and 2.6% nitrogen).
As was written, operational quantities are measurable unlike an effective dose, and instruments for radiation monitoring are calibrated in terms of these quantities. In monitoring, the values of these operational quantities are taken as a sufficiently precise assessment of effective dose and skin dose, respectively, in particular, if their values are below the protection limits. Numerical links between operational quantities and effective dose is represented by conservative conversion coefficients, which are defined for a reference person. In most practical situations, dosimeters provide reasonable approximations to the personal dose equivalent, Hp(d), at least at the location of the dosimeter. It must be noted, the personal dose equivalent generally overestimates the effective dose. On the other hand, this procedure is valid only at low doses and under the assumption of a uniform whole-body exposure. For high personal doses approaching or exceeding the annual dose limit, or in strongly inhomogeneous radiation fields, however, this procedure might not be sufficient.
Dose limits are split into two groups, the public, and occupationally exposed workers. According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Occupational Exposure – Effective Dose
In most situations of occupational exposure the effective dose, E, can be derived from operational quantities using the following formula:
The committed dose is a dose quantity that measures the stochastic health risk due to an intake of radioactive material into the human body.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Monitoring
We hope, this article, Personal Dose Equivalent – Hp(10) – Hp(0.07), helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Occupational Exposure. Generally, occupational radiation protection is the protection of workers in situations where their exposure is directly related to or required by their work. Radiation Dosimetry
Generally, occupational radiation protection is the protection of workers in situations where their exposure is directly related to or required by their work.
According to ICRP, occupational exposure refers to all exposure incurred by workers in the course of their work, with the exception of
excluded exposures and exposures from exempt activities involving radiation or exempt sources
any medical exposure
the normal local natural background radiation.
Quantities for Occupational Exposure
The ICRP also defines operational quantities for area and individual monitoring of external exposures. The operational quantities for area monitoring are:
Ambient dose equivalent, H*(10). The ambient dose equivalent is an operational quantity for area monitoring of strongly penetrating radiation.
Directional dose equivalent, H’ (d,Ω). The directional dose equivalent is an operational quantity for area monitoring of weakly penetrating radiation.
The operational quantities for individual monitoring are:
Personal dose equivalent, Hp(0.07). The Hp(0.07) dose equivalent is an operational quantity for individual monitoring for the assessment of the dose to the skin and to the hands and feet.
Personal dose equivalent, Hp(10). The Hp(10) dose equivalent is an operational quantity for individual monitoring for the assessment of effective dose.
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Dose limits are split into two groups, the public, and occupationally exposed workers.
The following table summarizes dose limits for occupationally exposed workers and for the public:
Table of dose limits for occupationally exposed workers and for the public. Source of data: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
According to the recommendation of the ICRP in its statement on tissue reactions of 21. April 2011, the equivalent dose limit for the lens of the eye for occupational exposure in planned exposure situations was reduced from 150 mSv/year to 20 mSv/year, averaged over defined periods of 5 years, with no annual dose in a single year exceeding 50 mSv.
Limits on effective dose are for the sum of the relevant effective doses from external exposure in the specified time period and the committed effective dose from intakes of radionuclides in the same period. For adults, the committed effective dose is computed for a 50-year period after intake, whereas for children it is computed for the period up to age 70 years. The effective whole-body dose limit of 20 mSv is an average value over five years. The real limit is 100 mSv in 5 years, with not more than 50 mSv in any one year.
Occupational Exposure – Effective Dose
In most situations of occupational exposure the effective dose, E, can be derived from operational quantities using the following formula:
The committed dose is a dose quantity that measures the stochastic health risk due to an intake of radioactive material into the human body.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Monitoring
We hope, this article, Occupational Exposure – Limits and Definition, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Deep Dose Equivalent – Shallow Dose Equivalent. Hp(0.07) is also called the shallow dose equivalent. For the assessment of deep organs and the control of effective dose, Hp(10) with a depth d = 10 mm is chosen. Hp(10) is also called the deep dose equivalent. Radiation Dosimetry
In general, the ICRP defines operational quantities for area and individual monitoring of external exposures. The operational quantities for area monitoring are:
Ambient dose equivalent, H*(10). The ambient dose equivalent is an operational quantity for area monitoring of strongly penetrating radiation.
Directional dose equivalent, H’ (d,Ω). The directional dose equivalent is an operational quantity for area monitoring of weakly penetrating radiation.
The operational quantities for individual monitoring are:
Personal dose equivalent, Hp(0.07). The Hp(0.07) dose equivalent is an operational quantity for individual monitoring for the assessment of the dose to the skin and to the hands and feet.
Personal dose equivalent, Hp(10). The Hp(10) dose equivalent is an operational quantity for individual monitoring for the assessment of effective dose.
Special Reference: ICRP, 2007. The 2007 Recommendations of the International Commission on Radiological Protection. ICRP Publication 103. Ann. ICRP 37 (2-4).
Deep Dose Equivalent and Shallow Dose Equivalent
Personal Dose Equivalent – Hp(10) – Hp(0.07)
Generally, the personal dose equivalent, Hp(d), is an operational quantity for individual monitoring. According to the ICRP, the personal dose equivalent is defined as:
ICRP Publication 103:
“The dose equivalent in soft tissue (commonly interpreted as the ‘ICRU sphere’) at an appropriate depth, d, below a specified point on the human body. ”
The personal dose equivalent is given the symbol Hp(d). Two common operational quantities for individual monitoring defined by the ICRP are:
Personal dose equivalent, Hp(0.07). The Hp(0.07) dose equivalent is an operational quantity for individual monitoring for the assessment of the dose to the skin and to the hands and feet.
Personal dose equivalent, Hp(10). The Hp(10) dose equivalent is an operational quantity for individual monitoring for the assessment of effective dose.
As can be seen, various depths can be used. The personal dose equivalent, Hp(d), can be assessed indirectly with a thin, tissue equivalent detector (radiation dosimeter) that is worn at the surface of the body and covered with an appropriate thickness of tissue equivalent material. The specified point, d, is normally taken to be where the radiation dosimeter is worn.
For assessment of superficial organs and the control of equivalent dose, depths of 0.07 mm for skin and 3 mm for the lens of the eye are employed, and the personal dose equivalents for those depths are denoted by Hp(0.07) and Hp(3), respectively. Hp(0.07) is also called the shallow dose equivalent.
For the assessment of deep organs and the control of effective dose, Hp(10) with a depth d = 10 mm is chosen. Hp(10) is also called the deep dose equivalent. If the personal dosimeter is worn on a position of the body representative of its exposure, at low doses and under the assumption of a uniform whole-body exposure, the value of Hp(10) provides an effective dose value sufficiently precise for radiological protection purposes. Neutron and gamma radiations contribute to both deep and shallow dose, but beta radiation is completely absorbed in the skin and therefore contributes to shallow dose only.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Monitoring
We hope, this article, Deep Dose Equivalent – Shallow Dose Equivalent, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Kerma vs Absorbed Dose. Kerma is related to, but not the same as absorbed dose. Absorbed dose is defined as the amount of energy deposited by ionizing radiation in a substance. Kerma is defined as the sum of the initial kinetic energies of all the charged particles liberated by uncharged ionizing radiation in a substance. Radiation Dosimetry
Absorbed Dose
Absorbed dose is defined as the amount of energy deposited by ionizing radiation in a substance. Absorbed dose is given the symbol D. The absorbed dose is usually measured in a unit called the gray (Gy), which is derived from the SI system. The non-SI unit rad is sometimes also used, predominantly in the USA.
Units of absorbed dose:
Gray. A dose of one gray is equivalent to a unit of energy (joule) deposited in a kilogram of a substance.
RAD. A dose of one rad is equivalent to the deposition of one hundred ergs of energy in one gram of any material.
A dose of one gray is equivalent to a unit of energy (joule) deposited in a kilogram of a substance. This unit was named in honour of Louis Harold Gray, who was one of the great pioneers in radiation biology. One gray is a large amount of absorbed dose. A person who has absorbed a whole body dose of 1 Gy has absorbed one joule of energy in each kg of body tissue.
Kerma
Kerma is a measure of kinetic energy transferred from radiation to matter. It is an acronym for “kinetic energy released per unit mass”. Kerma is given the symbol K and it is measured by the SI unit, the gray. This unit was named in honour of Louis Harold Gray, who was one of the great pioneers in radiation biology. Kerma is defined by the formula:
Kerma vs Absorbed Dose
Kerma is related to, but not the same as absorbed dose. Absorbed dose is defined as the amount of energy deposited by ionizing radiation in a substance. Kerma is defined as the sum of the initial kinetic energies of all the charged particles liberated by uncharged ionizing radiation in a substance. At low energies, kerma approximately equals absorbed dose, since most of initial kinetic energies of all the charged particles deposit their energy in the sample. At higher energies kerma is larger than absorbed dose because some highly energetic secondary electrons and X-rays escape the region of interest before depositing their energy. The escaping energy is counted in kerma, but not in absorbed dose. Note that there are three key interaction mechanisms of gamma rays with matter.
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Protection
We hope, this article, Kerma vs Absorbed Dose, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
This article summarizes key formulas and equations for calculation of the absorbed dose and the absorbed dose rate. Absorbed Dose – Formula – Equation
Absorbed Dose – Equation
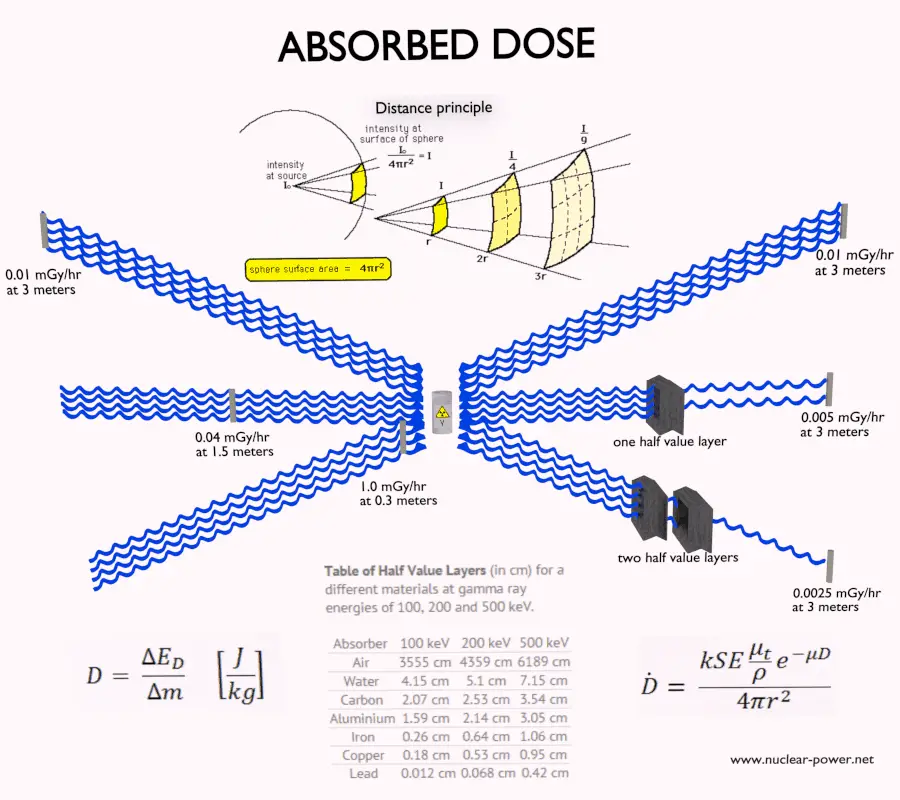
Absorbed dose is defined as the amount of energy deposited by ionizing radiation in a substance. Absorbed dose is given the symbol D. The absorbed dose is usually measured in a unit called the gray (Gy), which is derived from the SI system. The non-SI unit rad is sometimes also used, predominantly in the USA.
Units of absorbed dose:
Gray. A dose of one gray is equivalent to a unit of energy (joule) deposited in a kilogram of a substance.
RAD. A dose of one rad is equivalent to the deposition of one hundred ergs of energy in one gram of any material.
Absorbed Dose Rate – Equation
The absorbed dose rate is the rate at which an absorbed dose is received. It is a measure of radiation dose intensity (or strength). The absorbed dose rate is therefore defined as:
In conventional units, it is measured in mrad/sec, rad/hr, mGy/sec or Gy/hr. Since the amount of radiation exposure depends directly (linearly) on the time people spend near the source of radiation, the absorbed dose is equal to the strength of the radiation field (dose rate) multiplied by the length of time spent in that field. The example above indicates a person could expect to receive a dose of 25 millirems by staying in a 50 millirems/hour field for thirty minutes.
Absorbed Dose Rate Calculation
Assume the point isotropic source which contains 1.0 Ci of 137Cs, which has a half-life of 30.2 years. Note that the relationship between half-life and the amount of a radionuclide required to give an activity of one curie is shown below. This amount of material can be calculated using λ, which is the decay constant of certain nuclide:
About 94.6 percent decays by beta emission to a metastable nuclear isomer of barium: barium-137m. The main photon peak of Ba-137m is 662 keV. For this calculation, assume that all decays go through this channel.
Determine the primary photon dose rate, in gray per hour (Gy.h-1), at the outer surface of a 5 cm thick lead shield. Primary photon dose rate neglects all secondary particles. Assume that the effective distance of the source from the dose point is 10 cm. We shall also assume that the dose point is soft tissue and it can reasonably be simulated by water and we use the mass energy absorption coefficient for water.
The primary photon dose rate is attenuated exponentially, and the dose rate from primary photons, taking account of the shield, is given by:
As can be seen, we do not account for the buildup of secondary radiation. If secondary particles are produced or if the primary radiation changes its energy or direction, then the effective attenuation will be much less. This assumption generally underestimates the true dose rate, especially for thick shields and when the dose point is close to the shield surface, but this assumption simplifies all calculations. For this case the true dose rate (with the buildup of secondary radiation) will be more than two times higher.
To calculate the absorbed dose rate, we have to use in the formula:
k = 5.76 x 10⁻⁷
S = 3.7 x 10¹⁰ s-1
E = 0.662 MeV
μt/ρ = 0.0326 cm2/g (values are available at NIST)
μ = 1.289 cm-1 (values are available at NIST)
D = 5 cm
r = 10 cm
Result:
The resulting absorbed dose rate in grays per hour is then:
If we want to account for the buildup of secondary radiation, then we have to include the buildup factor. The extended formula for the dose rate is then:
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Absorbed Dose
We hope, this article, Absorbed Dose – Formula – Equation, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
Equivalent dose (symbol HT) is a dose quantity calculated for individual organs (index T – tissue). Equivalent dose is based on the absorbed dose to an organ, adjusted to account for the effectiveness of the type of radiation. Radiation Dosimetry
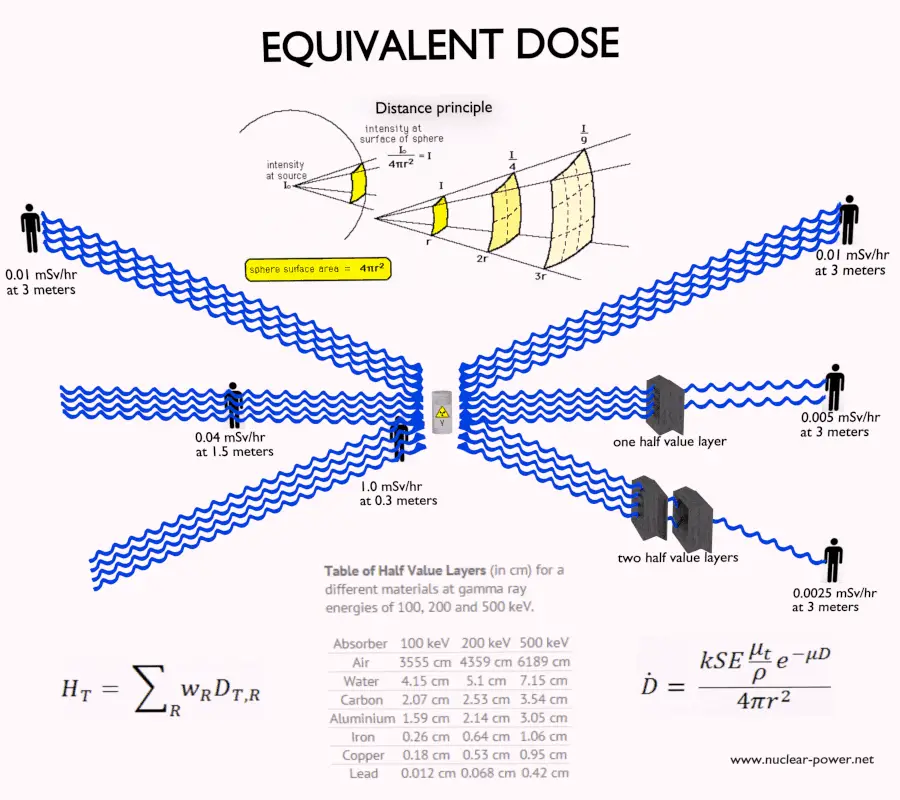
Equivalent dose (symbol HT) is a dose quantity calculated for individual organs (index T – tissue). Equivalent dose is based on the absorbed dose to an organ, adjusted to account for the effectiveness of the type of radiation. Equivalent dose is given the symbol HT. The SI unit of HT is the sievert (Sv) or but rem (roentgen equivalent man) is still commonly used (1 Sv = 100 rem). Unit of sievert was named after the Swedish scientist Rolf Sievert, who did a lot of the early work on dosimetry in radiation therapy.
As was written, for radiation protection purposes, the absorbed dose is averaged over an organ or tissue, T, and this absorbed dose average is weighted for the radiation quality in terms of the radiation weighting factor, wR, for the type and energy of radiation incident on the body. The radiation weighting factor is a dimensionless factor used to determine the equivalent dose from the absorbed dose averaged over a tissue or organ and is based on the type of radiation absorbed. The resulting weighted dose was designated as the organ- or tissue equivalent dose:
An equivalent dose of one Sievert represents that quantity of radiation dose that is equivalent, in terms of specified biological damage, to one gray of X-rays or gamma rays. Equivalent dose is a non-physical quantity (wR is derived from biological consequences of ionizing radiation) widely used in dosimetry measured by dosimeters. Equivalent dose is designated by the ICRP as a “limiting quantity”; to specify exposure limits to ensure that “the occurrence of stochastic health effects is kept below unacceptable levels and that tissue reactions are avoided”.
Equivalent dose, HT, is used for assessing stochastic health risk due to external radiation fields that penetrate uniformly through the whole body. However it needs further corrections when the field is applied only to part(s) of the body, or non-uniformly to measure the overall stochastic health risk to the body. To enable this a further dose quantity called effective dose must be used. Effective dose is defined as the sum of the organ-equivalent doses weighted by the ICRP organ weighting factors, wT, which takes into account the varying sensitivity of different organs and tissues to radiation.
Units of equivalent dose:
Sievert. The sievert is a derived unit of equivalent dose and effective dose and for represents the equivalent biological effect of the deposit of a joule of gamma rays energy in a kilogram of human tissue.
REM. The rem (an abbreviation for Roentgen Equivalent Man) is the non-SI unit of the equivalent dose, which is used predominantly in the USA. It is a term for dose equivalence and equals the biological damage that would be caused by one rad of dose.
A dose of one Sv caused by gamma radiation is equivalent to an energy deposition of one joule in a kilogram of a tissue. That means one sievert is equivalent to one gray of gamma rays deposited in certain tissue. On the other hand, similar biological damage (one sievert) can be caused only by 1/20 gray of alpha radiation.
One sievert is a large amount of equivalent dose. A person who has absorbed a whole body dose of 1 Sv has absorbed one joule of energy in each kg of body tissue (in case of gamma rays).
Equivalent doses measured in industry and medicine often have usually lower doses than one sievert, and the following multiples are often used:
1 mSv (millisievert) = 1E-3 Sv
1 µSv (microsievert) = 1E-6 Sv
Conversions from the SI units to other units are as follows:
1 Sv = 100 rem
1 mSv = 100 mrem
From Absorbed Dose to Equivalent Dose
Note that the sievert is not a physical dose unit. For example, an absorbed dose of 1 Gy by alpha particles will lead to an equivalent dose of 20 Sv. This may seem to be a paradox. It implies that the energy of the incident radiation field in joules has increased by a factor of 20, thereby violating the laws of Conservation of energy. However, this is not the case. Sievert is derived from the physical quantity absorbed dose, but also takes into account the biological effectiveness of the radiation, which is dependent on the radiation type and energy. The radiation weighting factor causes that the sievert cannot be a physical unit.
As was written, each type of radiation interacts with matter in a different way and causes different biological damages. For example charged particles with high energies can directly ionize atoms. On the other hand electrically neutral particles interacts only indirectly, but can also transfer some or all of their energies to the matter. It would certainly simplify matters if biological effects of radiation were directly proportional to the absorbed dose. Unfortunately, biological effects depend also on the way in which the absorbed dose is distributed along the path of the radiation. Studies have shown that alpha and neutron radiation cause greater biological damage for a given energy deposition per kg of tissue than gamma radiation does. It was discovered, biological effects of any radiation increases with the linear energy transfer (LET). In short, the biological damage from high-LET radiation (alpha particles, protons or neutrons) is much greater than that from low-LET radiation (gamma rays). This is because the living tissue can more easily repair damage from radiation that is spread over a large area than that which is concentrated in a small area. Because more biological damage is caused for the same physical dose (i.e., the same energy deposited per unit mass of tissue), one gray of alpha or neutron radiation is more harmful than one gray of gamma radiation. This fact that radiations of different types (and energies) give different biological effects for the same absorbed dose is described in terms of factors known as the relative biological effectiveness (RBE) and the radiation weighting factor (wR).
Radiation Weighting Factor
In radiation protection, the radiation weighting factor is a dimensionless factor used to determine the equivalent dose from the absorbed dose averaged over a tissue or organ and is based on the type of radiation absorbed. In the past there a similar factor known as quality factor was used for this purpose. The radiation weighting factor is an estimate of the effectiveness per unit dose of the given radiation relative a to low-LET standard.
Before 1990, dose-equivalent quantities were defined in terms of a quality factor, Q(L), that was applied to the absorbed dose at a point in order to take into account the differences in the effects of different types of radiation. In its 1990 recommendations, the ICRP introduced a modified concept. For radiological protection purposes, the absorbed dose is averaged over an organ or tissue, T, and this absorbed dose average is weighted for the radiation quality in terms of the radiation weighting factor, wR, for the type and energy of radiation incident on the body.
The reason for replacing the quality factor, i.e. the Q–L relationship, with wR values in the definition of the organ-equivalent doses and the effective dose was that the Commission believed:
‘that the detail and precision inherent in using a formal Q–L relationship to modify absorbed dose to reflect the higher probability of detriment resulting from exposure to radiation components with high LET is not justified because of the uncertainties in the radiological information’.
Noteworthy, these two factors, the radiation weighting factor and the quality factor are restricted to the dose range of interest to radiation protection, i.e. to the general magnitude of the dose limits. In special circumstances where one deals with higher doses that can cause deterministic effects, the relevant RBE values are applied to obtain a weighted dose.
Special Reference: ICRP, 2003. Relative Biological Effectiveness (RBE), Quality Factor (Q), and Radiation Weighting Factor (wR). ICRP Publication 92. Ann. ICRP 33 (4).
Radiation Weighting Factors – ICRP
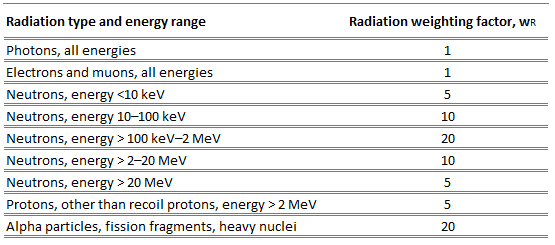
For photon and electron radiation, the radiation weighting factor has the value 1 independently of the energy of the radiation and for alpha radiation the value 20. For neutron radiation, the value is energy-dependent and amounts to 5 to 20.
In 2007 ICRP published a new set of radiation weighting factors (ICRP Publ. 103: The 2007 Recommendations of the International Commission on Radiological Protection). These factors are given below.
Source: ICRP, 2007. Publ. 103: The 2007 Recommendations of the International Commission on Radiological Protection.
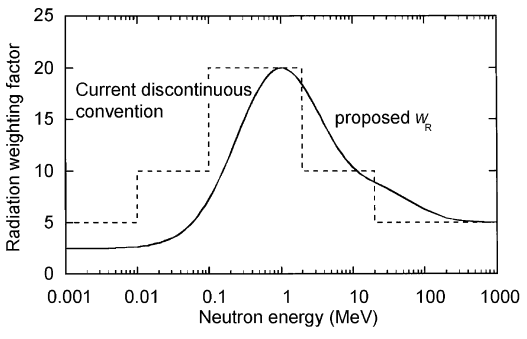
As shown in the table, a wR of 1 is for all low-LET radiations, i.e. X-rays and gamma rays of all energies as well as electrons and muons. A smooth curve, considered an approximation, was fitted to the wR values as a function of incident neutron energy. Note that En is the neutron energy in MeV.
The radiation weighting factor wR for neutrons introduced in Publication 60 (ICRP, 1991) as a discontinuous function of the neutron energy(- – -) and the proposed modification (—).
Thus for example, an absorbed dose of 1 Gy by alpha particles will lead to an equivalent dose of 20 Sv, and an equivalent dose of radiation is estimated to have the same biological effect as an equal amount of absorbed dose of gamma rays, which is given a weighting factor of 1.
Quality Factor
The quality factor of a radiation type is defined as the ratio of the biological damage produced by the absorption of 1 Gy of that radiation to the biological damage produced by 1 Gy of X-rays or gamma rays.
The Q of a certain type of radiation is related to the density of the ion tracks it leaves behind it in tissue. The quality factors for the various types of radiation are listed in the table.
These quality factors are restricted to the dose range of interest to radiation protection, i.e. to the general magnitude of the dose limits. In special circumstances where one deals with higher doses that can cause deterministic effects, the relevant RBE values are applied to obtain a weighted dose.
Examples of Doses in Sieverts
We must note that radiation is all around us. In, around, and above the world we live in. It is a natural energy force that surrounds us. It is a part of our natural world that has been here since the birth of our planet. In the following points we try to express enormous ranges of radiation exposure, which can be obtained from various sources.
0.05 µSv – Sleeping next to someone
0.09 µSv – Living within 30 miles of a nuclear power plant for a year
0.1 µSv – Eating one banana
0.3 µSv – Living within 50 miles of a coal power plant for a year
10 µSv – Average daily dose received from natural background
20 µSv – Chest X-ray
40 µSv – A 5-hour airplane flight
600 µSv – mammogram
1 000 µSv – Dose limit for individual members of the public, total effective dose per annum
3 650 µSv – Average yearly dose received from natural background
5 800 µSv – Chest CT scan
10 000 µSv – Average yearly dose received from natural background in Ramsar, Iran
20 000 µSv – single full-body CT scan
175 000 µSv – Annual dose from natural radiation on a monazite beach near Guarapari, Brazil.
5 000 000 µSv – Dose that kills a human with a 50% risk within 30 days (LD50/30), if the dose is received over a very short duration.
As can be seen, low-level doses are common for everyday life. The previous examples can help illustrate relative magnitudes. From biological consequences point of view, it is very important to distinguish between doses received over short and extended periods. An “acute dose” is one that occurs over a short and finite period of time, while a “chronic dose” is a dose that continues for an extended period of time so that it is better described by a dose rate. High doses tend to kill cells, while low doses tend to damage or change them. Low doses spread out over long periods of time don’t cause an immediate problem to any body organ. The effects of low doses of radiation occur at the level of the cell, and the results may not be observed for many years.
Equivalent Dose Rate
The equivalent dose rate is the rate at which an equivalent dose is received. It is a measure of radiation dose intensity (or strength). The equivalent dose rate is therefore defined as:
In conventional units, it is measured in mSv/sec, Sv/hr, mrem/sec or rem/hr. Since the amount of radiation exposure depends directly (linearly) on the time people spend near the source of radiation, the absorbed dose is equal to the strength of the radiation field (dose rate) multiplied by the length of time spent in that field. The example above indicates a person could expect to receive a dose of 25 millirems by staying in a 50 millirems/hour field for thirty minutes.
Calculation of Shielded Dose Rate
Assume the point isotropic source which contains 1.0 Ci of 137Cs, which has a half-life of 30.2 years. Note that the relationship between half-life and the amount of a radionuclide required to give an activity of one curie is shown below. This amount of material can be calculated using λ, which is the decay constant of certain nuclide:
About 94.6 percent decays by beta emission to a metastable nuclear isomer of barium: barium-137m. The main photon peak of Ba-137m is 662 keV. For this calculation, assume that all decays go through this channel.
Calculate the primary photon dose rate, in gray per hour (Gy.h-1), at the outer surface of a 5 cm thick lead shield. Then calculate theequivalent dose rate. Assume that this external radiation field penetrate uniformly through the whole body. Primary photon dose rate neglects all secondary particles. Assume that the effective distance of the source from the dose point is 10 cm. We shall also assume that the dose point is soft tissue and it can reasonably be simulated by water and we use the mass energy absorption coefficient for water.
The primary photon dose rate is attenuated exponentially, and the dose rate from primary photons, taking account of the shield, is given by:
As can be seen, we do not account for the buildup of secondary radiation. If secondary particles are produced or if the primary radiation changes its energy or direction, then the effective attenuation will be much less. This assumption generally underestimates the true dose rate, especially for thick shields and when the dose point is close to the shield surface, but this assumption simplifies all calculations. For this case the true dose rate (with the buildup of secondary radiation) will be more than two times higher.
To calculate the absorbed dose rate, we have to use in the formula:
k = 5.76 x 10⁻⁷
S = 3.7 x 10¹⁰ s-1
E = 0.662 MeV
μt/ρ = 0.0326 cm2/g (values are available at NIST)
μ = 1.289 cm-1 (values are available at NIST)
D = 5 cm
r = 10 cm
Result:
The resulting absorbed dose rate in grays per hour is then:
Since the radiation weighting factor for gamma rays is equal to one and we have assumed the uniform radiation field, we can directly calculate the equivalent dose rate from the absorbed dose rate as:
If we want to account for the buildup of secondary radiation, then we have to include the buildup factor. The extended formula for the dose rate is then:
Robert Reed Burn, Introduction to Nuclear Reactor Operation, 1988.
U.S. Department of Energy, Nuclear Physics and Reactor Theory. DOE Fundamentals Handbook, Volume 1 and 2. January 1993.
Paul Reuss, Neutron Physics. EDP Sciences, 2008. ISBN: 978-2759800414.
See also:
Radiation Protection
We hope, this article, Equivalent Dose, helps you. If so, give us a like in the sidebar. Main purpose of this website is to help the public to learn some interesting and important information about radiation and dosimeters.
 In general, the ICRP defines operational quantities for area and individual monitoring of external exposures. The operational quantities for area monitoring are: